




METABOLITE 6 (KW-6356) 30ML LIQUID (6MG/ML, 180MG BOTTLE)
$49.99
Metabolite 6 (KW-6356) is sold for laboratory research use only. Terms of sale apply. Not for human consumption, nor medical, veterinary, or household uses. Please familiarize yourself with our Terms & Conditions prior to ordering.


Also Available In:
 Capsule Option >> Powder Option >>
- Description
- Additional information
Description
Metabolite 6 (KW-6356) Nootropic Liquid








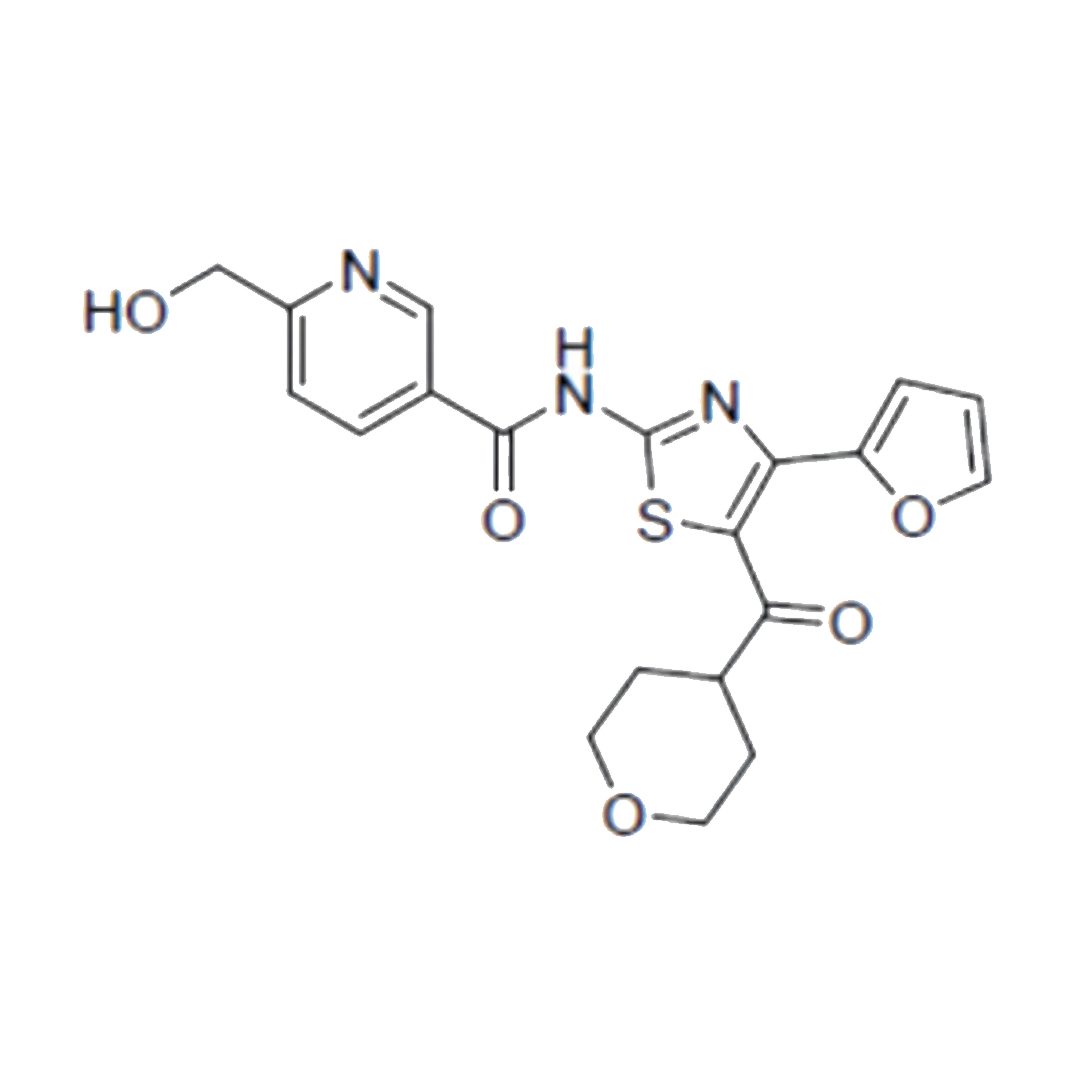
| CAS Number | 858979-50-7 |
| Other Names | M6, Metabolite6, Metabolite 6, KW-6356, KW6356, KW 6356 |
| IUPAC Name |
N-[4-(2-furyl)-5-(3,4,5,6-tetrahydro-2H-pyran-4-ylcarbonyl)-1,3-thiazol-2-yl]-6-(hydroxymethyl)pyrid
|
| Molecular Formula | C₂₀H₁₉N₃O₄S |
| Molecular Weight | 397.45 |
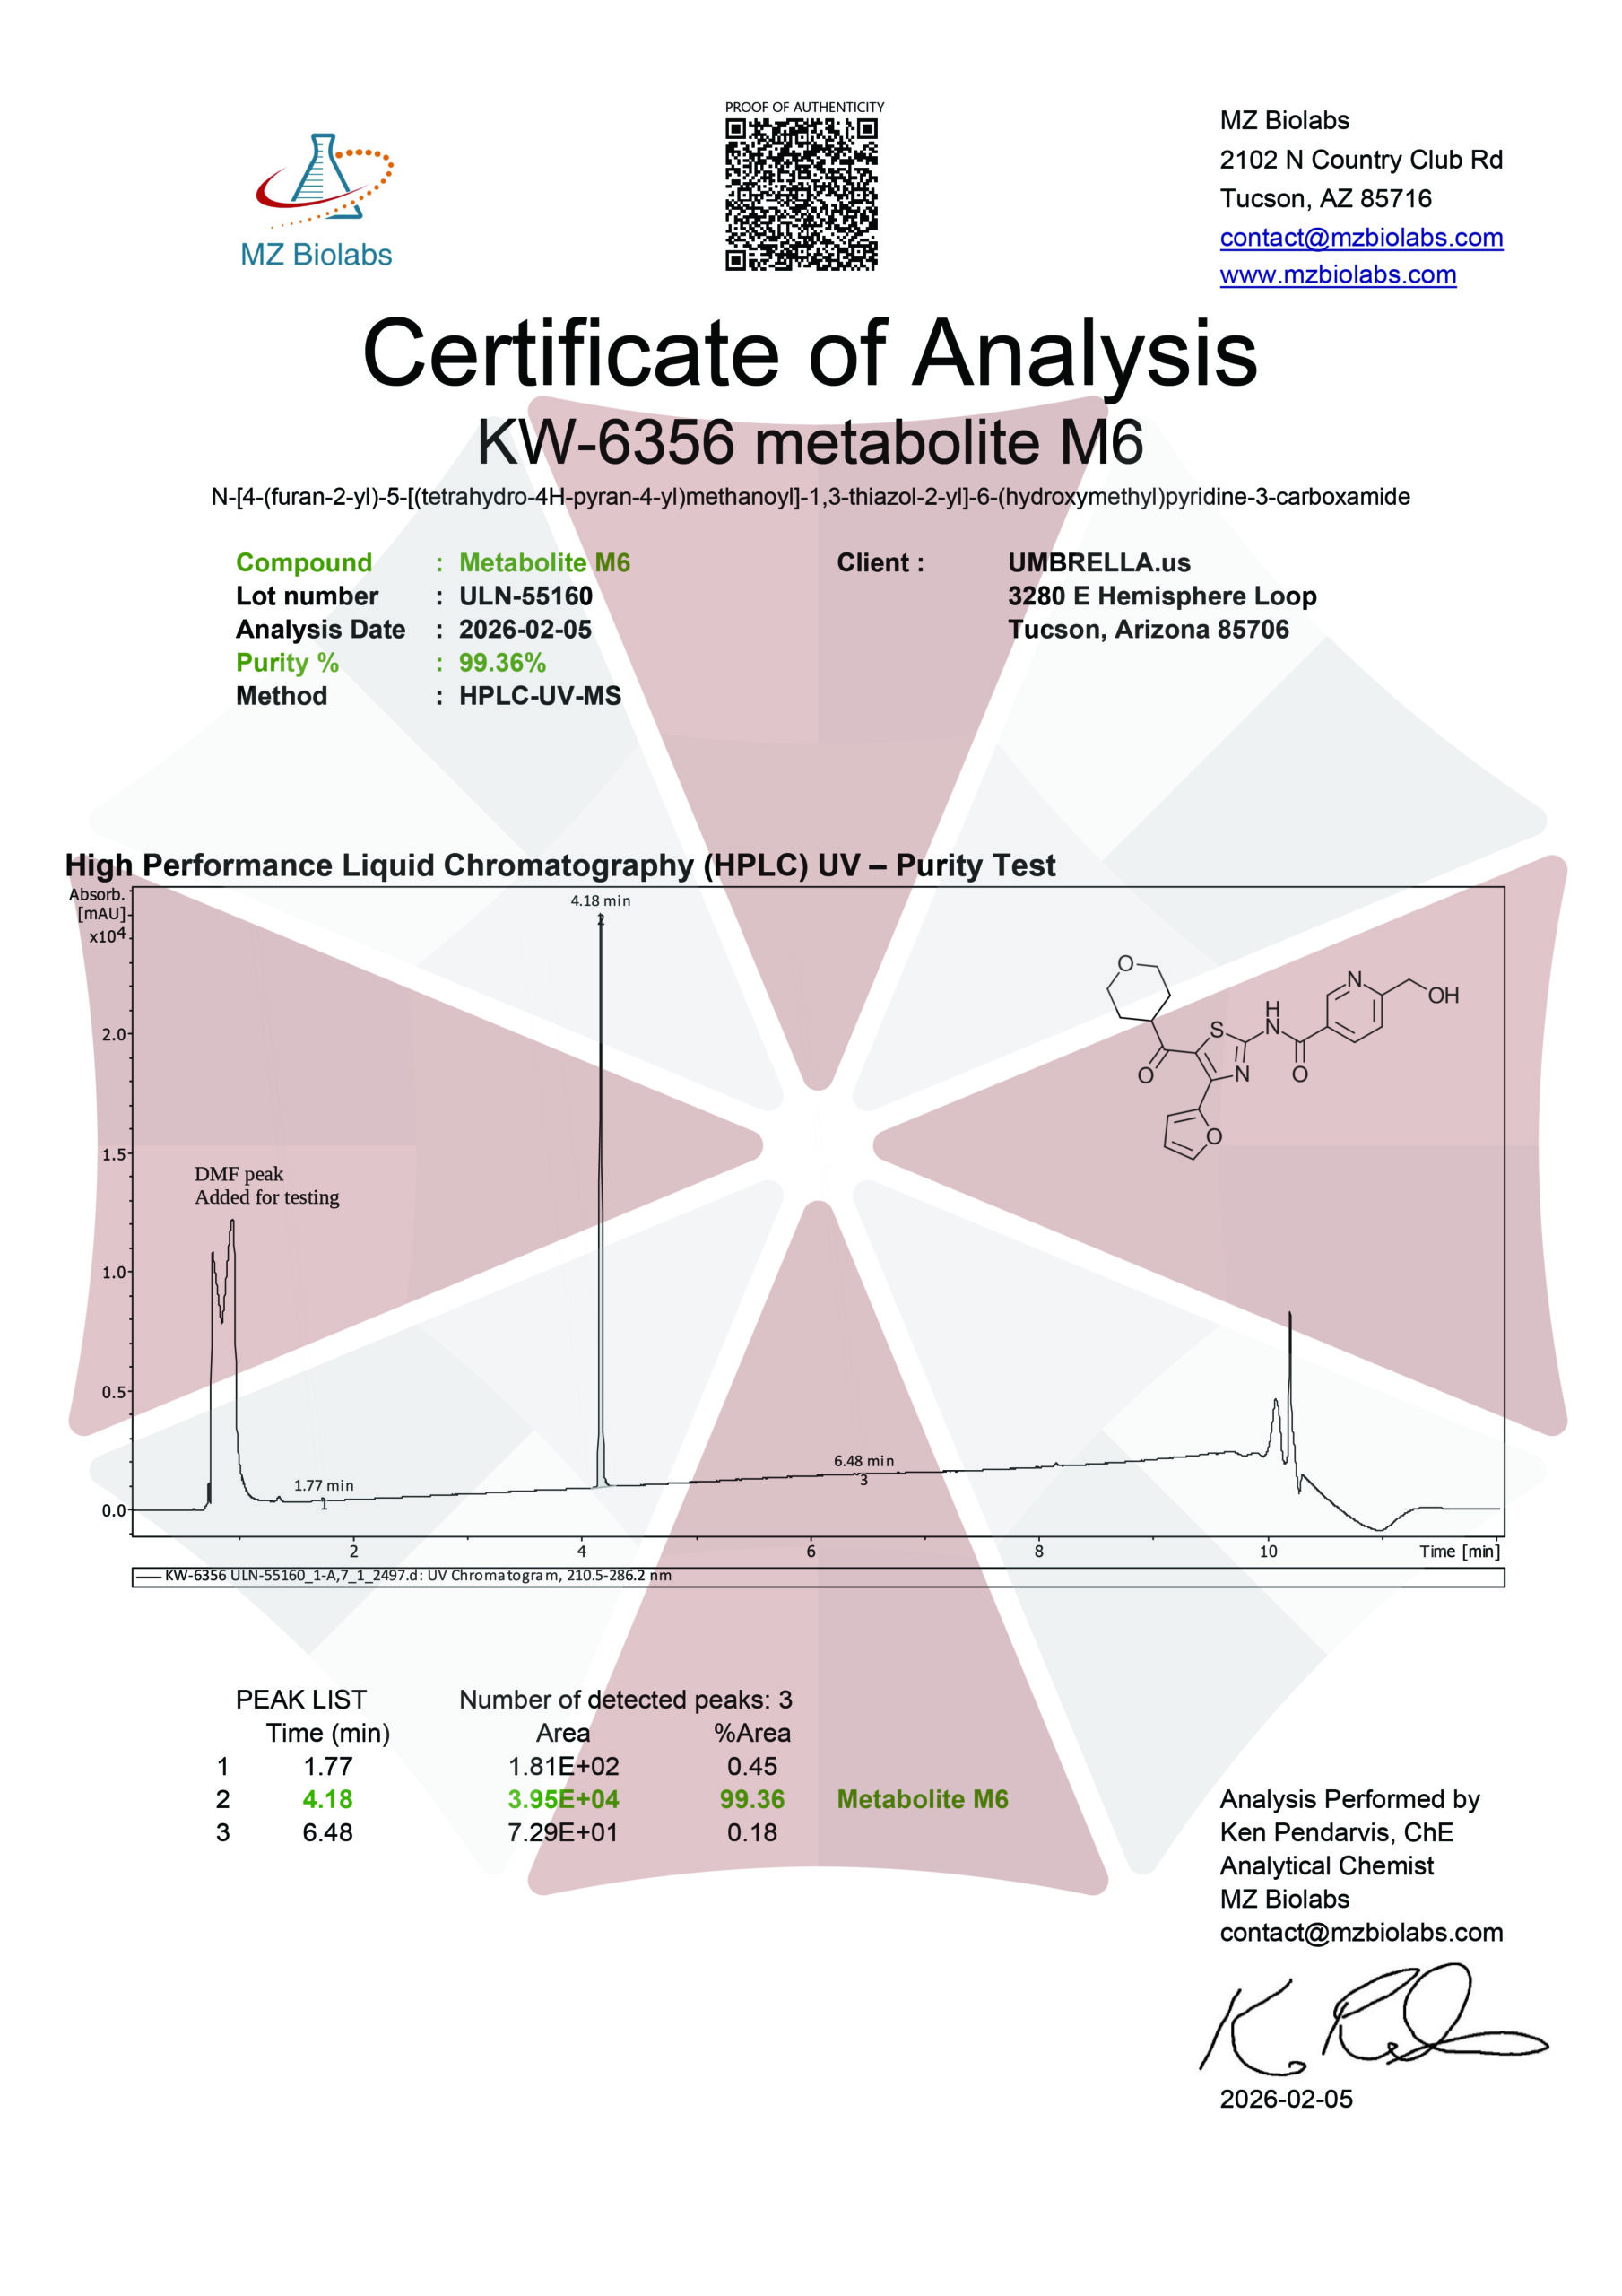
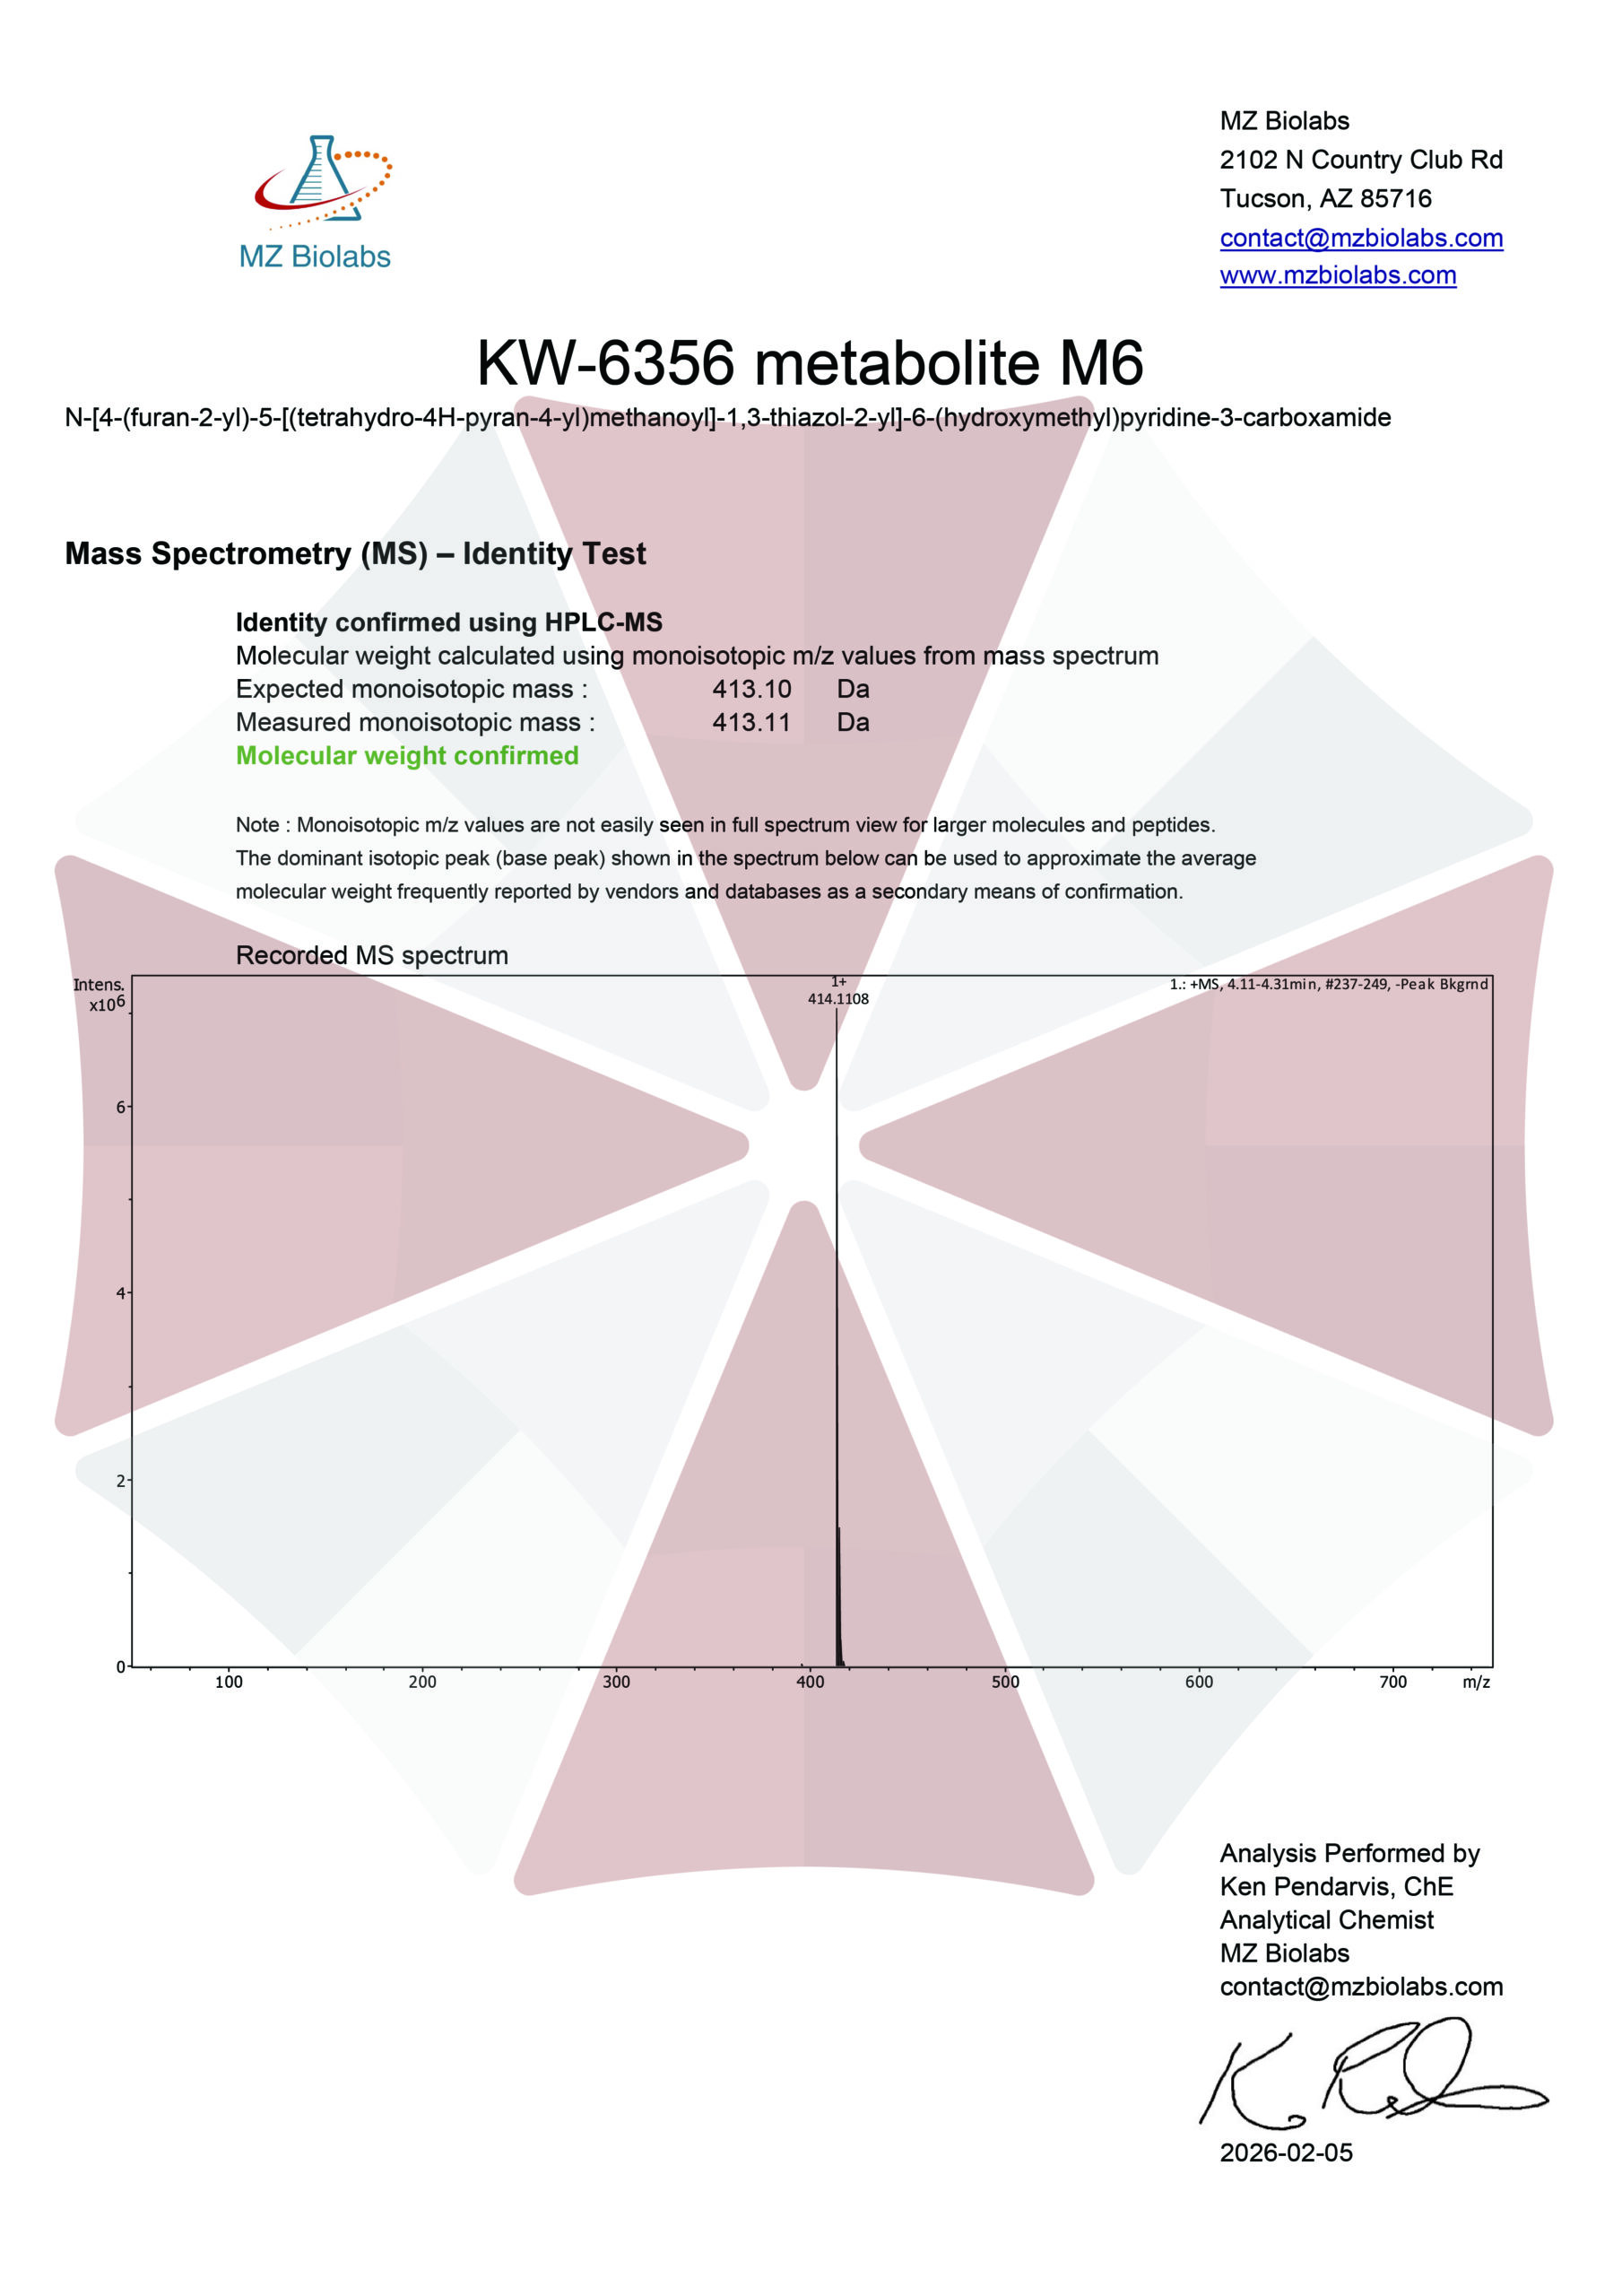
| Purity | ≥99% Pure (LC-MS) |
| Liquid Availability | 30mL liquid (6mg/mL, 180mg bottle) |
| Powder Availability | 60 capsules (6mg/capsule, 360mg total)
|
| Storage | Store in cool dry environment, away from direct sunlight. |
| Terms | All products are for laboratory developmental research USE ONLY. Products are not for human consumption. |
What is Metabolite 6?
Metabolite 6, commonly referred to as KW-6356, is a small-molecule nootropic reportedly developed to enhance cognitive function by modulating neuronal signaling and supporting neuroprotective pathways. Preclinical studies and early-stage research describe effects such as improved synaptic plasticity, memory performance, and resilience to neurotoxic stress, with current research focused on clarifying the precise mechanisms of action of the compound.
Main Research Findings
1) Treatment with Metabolite 6 was well-tolerated and resulted in improved scores on the MDS-UPDRS Parts II and III in a model of Parkinson’s Disease
2) Metabolite 6 was found to enhance the anti-parkinsonian activity of L-DOPA while exhibiting a low risk of secondary dyskinesia.
Selected Data
1) This study conducted by the research team of Maeda et al was designed as a multicenter, randomized, placebo-controlled, and double-blind trial aiming to assess the efficacy and safety of Metabolite 6 (KW-6356) monotherapy in patients with early, untreated Parkinson’s disease (PD). The investigational compound, KW-6356, is a novel, selective adenosine A2A receptor antagonist/inverse agonist [1].
The study population comprised male or female patients aged 20-80 years, diagnosed with PD according to the UK Brain Bank Criteria, presenting with a Modified Hoehn and Yahr stage of I-III, and having a Movement Disorder Society version Unified PD Rating Scale (MDS-UPDRS) Part III total score of at least 15. Strict inclusion and exclusion criteria were applied to ensure a homogeneous and untreated population. Key exclusion criteria included prior use of levodopa for more than 4 weeks, or any other PD medications such as dopamine agonists, COMT inhibitors, anticholinergics, droxidopa, or amantadine, within 4 weeks prior to enrollment, as well as MAO-B inhibitors/zonisamide within 3 months. Furthermore, concomitant treatment with CYP3A4/5-related drugs within 2 weeks, antipsychotics within 3-6 months, an MMSE score below 23, or any clinically significant coexisting medical condition (hepatic, renal, pancreatic, cardiovascular, endocrinologic, gastrointestinal, respiratory, neurologic other than PD) that could interfere with patient safety or study completion were also exclusion factors [1].
Following an extensive screening period of up to 8 weeks, eligible patients were randomized using a computer-generated scheme into one of three treatment groups in a 1:1:1 ratio, the groups were as follows: KW-6356 at 3 mg/day, KW-6356 at 6 mg/day, or a matched placebo. Study medication was administered orally, once daily, in the morning after breakfast, for a total duration of 12 weeks. Patient assessments were scheduled at baseline, and then at Weeks 2, 4, 8, and 12, with an additional safety follow-up assessment at Week 14.
The primary efficacy endpoint was defined as the least squares (LS) mean change from baseline to Week 12 in the MDS-UPDRS Part III total score, which evaluates motor symptoms. This primary endpoint was analyzed using an analysis of covariance (ANCOVA) model, incorporating the treatment group as a fixed effect and the baseline MDS-UPDRS Part III score as a covariate. Secondary efficacy endpoints included comprehensive assessments from the MDS-UPDRS Total score (sum of Parts I-III), MDS-UPDRS Part II + III score (motor experiences of daily living combined with motor examination), MDS-UPDRS Part I score (non-motor experiences of daily living), and MDS-UPDRS Part II score (motor experiences of daily living) [1].
These secondary endpoints were analyzed similarly to the primary outcome. Exploratory assessments included the 39-item PD questionnaire (PDQ-39) summary index and its domain scores (mobility, emotional well-being, stigma, social support, and communication), and both Clinical Global Impressions of Improvement (CGI-I) and Patient Global Impressions of Improvement (PGI-I), which were rated on 7-point scales at Week 12. For these exploratory analyses, results were summarized descriptively, as the study was not powered for hypothesis testing on these outcomes. Missing data for all efficacy measures were handled using the last observation carried forward (LOCF) method.
Safety was a critical aspect of the study, meticulously monitored at every visit. Routine physical and neurological examinations, standard laboratory tests, and electrocardiogram (ECG) recordings were also performed. Additionally, the Columbia Suicide Severity Rating Scale (C-SSRS) and the Mini-Mental State Examination (MMSE) were administered at baseline and Week 12 to capture potential neuropsychiatric effects. The per-protocol set (PPS), which included all patients who took study medication with a compliance of at least 80% and had an MDS-UPDRS Part III assessment at Week 12 without major protocol deviations, was used for efficacy analyses. The safety set encompassed all patients who received at least one dose of study medication [1].
2) This study performed by Ohno et al employed a comprehensive set of methods and materials to investigate the potential of Metabolite 6 (KW-6356), a novel selective adenosine A2A receptor antagonist/inverse agonist, to enhance the anti-parkinsonian activity of L-DOPA while mitigating dyskinesia. The research was conducted using common marmosets, an established animal model for Parkinson’s disease (PD), under strict ethical guidelines. Male and female marmosets, aged over two years at the study’s commencement, were housed in stainless steel cages under controlled environmental conditions including 25-29 °C, 20%-60% humidity, and a 12-hour light-dark cycle. They received ad libitum access to a specialized monkey diet and fresh water [2].
Parkinsonism was experimentally induced in the marmosets through subcutaneous administration of MPTP hydrochloride at a dose of 2.0 mg/kg once daily for 5 consecutive days, dissolved in physiological saline. To ensure consistent symptom development, some animals received additional MPTP injections approximately three weeks after the initial treatment, depending on their individual symptoms. Following MPTP administration, animals were hand-fed a specialized paste of pelleted diet, mashed fresh fruit, and liquid feed to aid their recovery from the acute effects of MPTP. A crucial selection criterion for participation in the studies was that animals exhibited clear PD-like symptoms and demonstrated a measurable response to L-DOPA at least six weeks after the initial MPTP dose.
To prepare for dyskinesia-related studies, a subset of MPTP-treated marmosets was primed for dyskinesia by orally administering L-DOPA at a dose of 10 mg/kg plus benserazide at a dose of 2.5 mg/kg twice daily for 28 days. Only those animals displaying a mean maximal dyskinesia score of ≥3.5, with individual scores ≥2, were selected for the dyskinesia studies. The investigational compound, KW-6356, was consistently administered at an optimal dose of 1 mg/kg. It was prepared as a suspension in 0.5% methyl cellulose and 10% sucrose solution. L-DOPA and benserazide, maintaining a fixed L-DOPA:benserazide ratio of 4, were prepared similarly as suspensions in 0.5% methyl cellulose and 10% sucrose. All drugs, including KW-6356, L-DOPA, and benserazide, were administered orally at a consistent volume of 2 mL/kg body weight [2].
The study design incorporated three distinct experimental studies to address different aspects of KW-6356’s therapeutic potential: Study 1aimed to evaluate the acute effects of KW-6356 monotherapy and its combination with various doses of L-DOPA/benserazide, ranging from 2.5/0.625 mg/kg to 10/2.5 mg/kg, on motor disability and locomotor activity in MPTP-treated marmosets that were not yet primed for dyskinesia (drug-naive). Study 2 investigated the acute effects of KW-6356 at a dose of 1 mg/kg, co-administered with different doses of L-DOPA/benserazide at doses of 1.25/0.312 mg/kg to 10/2.5 mg/kg, on both dyskinesia and locomotor activity in MPTP-treated marmosets that had been primed to exhibit dyskinesia. Study 3 explored the effects of chronic co-administration. Dyskinesia levels were first established using a high dose of L-DOPA at a dose of 10 mg/kg plus benserazide at a dose of 2.5 mg/kg as the “L-DOPA pre” value on Day -8. Subsequently, vehicle was administered to determine a control value (“L-DOPA post” on Day -1), followed by a low 2.5 mg/kg dose of L-DOPA plus 0.625 mg/kg of benserazide alone (“L-DOPA cont” on Day 0). Then, KW-6356 at a dose of 1 mg/kg was co-administered daily with this low-dose L-DOPA/benserazide regimen for 21 days. A one-week washout period followed this chronic treatment, and dyskinesia assessments were performed throughout [2].
Behavioral assessments were rigorous and standardized. Motor disability was continuously monitored for 6 hours post-drug administration using a one-way mirror and an established rating scale with scores ranging from 0 for minimal disability to 17 for severe. Locomotor activity was quantified by counting light beam interruptions in stainless steel cages equipped with photoelectric sensors, recording activity in 30-minute intervals for 8 or 12 hours post-drug. Dyskinesia was specifically assessed using a semi-quantitative scoring system with 0 being absent, to 4 being severe, for 3 or 6 hours post-drug, with the maximal intensity recorded during a 1-hour observation period.
Statistical analyses were performed using SAS software. For comparing mean values of total locomotor activities, paired t-tests were used for L-DOPA-only vs. L-DOPA + KW-6356 groups, and Dunnett tests for L-DOPA groups vs. vehicle. For total motor disability and maximal dyskinesia scores, the sign-Wilcoxon test was applied for paired comparisons, and the Steel test for multiple comparisons against the vehicle control. This comprehensive methodological approach allowed for a robust evaluation of KW-6356’s multifaceted effects in a preclinical model of PD [2].
Discussion
1) The study performed by Maeda et al successfully screened 185 patients, with 168 ultimately randomized and treated across the three study groups: placebo, KW-6356 3 mg/day, and KW-6356 6 mg/day. A total of 17 patients did not meet eligibility criteria. The per-protocol set, used for efficacy analyses, included 155 patients, representing 92.3% of the randomized population. Week 12 completion rates were high, exceeding 90% for all groups, with withdrawal of consent being the primary reason for discontinuation. Baseline demographics were largely comparable across groups, though the placebo group had a slightly higher proportion of male patients [1].
The primary efficacy endpoint, the LS mean change from baseline to Week 12 in MDS-UPDRS Part III total score, demonstrated significant improvement in both KW-6356 treatment groups compared to placebo. The 3 mg/day group showed an LS mean change of -5.37, and the 6 mg/day group showed -4.76, whereas the placebo group showed a change of -3.14. The LS mean differences versus placebo indicated greater improvements for KW-6356: -2.23 for the 3 mg/day group and -1.62 for the 6 mg/day group. Notably, changes from baseline were numerically larger for both KW-6356 groups than for placebo at all measured time points throughout the study.
Secondary efficacy endpoints consistently supported these primary findings. MDS-UPDRS subitem scores and total scores (including Parts I, II, and III) also showed greater reductions from baseline in both KW-6356 groups compared to placebo, with numerical improvements observed across all measured time points. Part IV (motor complication) scores were zero-rated for all patients due to the early stage of PD and the untreated status of the cohort. The PDQ-39 summary index showed modest improvements from baseline in the KW-6356 groups by -0.66 for 3 mg/day, and -0.92 for 6 mg/day, compared to a slight worsening in the placebo group by +0.81. Specific PDQ-39 domains, including mobility, emotional well-being, stigma, social support, and communication, also showed reductions in the KW-6356 treatment groups. Global impression of improvement (CGI-I) showed that 46.9% of patients in the 3 mg/day group and 51.9% in the 6 mg/day group were rated as improved, compared to 36.5% in the placebo group. Similarly, PGI-I indicated that 32.7% of patients in the 3 mg/day group and 37.0% in the 6 mg/day group felt better, versus 30.8% in the placebo group [1].
Regarding safety, the incidence of overall TEAEs and drug-related TEAEs was similar across all three groups with serious TEAEs occurring very rarely. No serious TEAEs were reported in the placebo or KW-6356 6 mg/day groups. Crucially, other safety endpoints, including laboratory parameters, vital signs, ECG, MMSE, and C-SSRS, showed no clinically significant changes across the treatment groups. Interestingly, the 3 mg/day dose of KW-6356 showed numerically greater efficacy in motor symptoms than the 6 mg/day dose, aligning with preclinical observations of diminishing additional benefits at higher doses. Overall, the study demonstrated that KW-6356 monotherapy was well-tolerated and more effective than placebo in patients with early, untreated PD [1].
2) The study conducted by the research team of Ohno et al yielded significant and nuanced results regarding the efficacy of KW-6356, an adenosine A2A receptor antagonist/inverse agonist, in improving motor symptoms and modulating dyskinesia in MPTP-treated common marmosets. The findings underscore KW-6356’s potential as a valuable therapeutic agent for PD treatment.
The results of the first study investigating the effects on motor disability and locomotor activity in drug-naive (not previously primed for dyskinesia) MPTP marmosets, found that oral administration of L-DOPA/benserazide alone exhibited a dose-dependent effect, leading to a reversal of motor disability and an increase in locomotor activity. Specifically, significant improvements in motor disability were observed at L-DOPA doses of 10/2.5 mg/kg. Locomotor activity was also significantly increased at L-DOPA doses of 7.5/1.875 mg/kg and 10/2.5 mg/kg. A key finding of this study was the potentiation of these anti-parkinsonian effects when 1 mg/kg of KW-6356 was co-administered with L-DOPA/benserazide. The combination significantly enhanced the L-DOPA-induced decrease in total disability score and robustly amplified the increase in total locomotor activity across a wide range of L-DOPA doses from 2.5/0.625 to 10/2.5 mg/kg. This suggests that KW-6356 can augment the therapeutic benefits of L-DOPA, potentially allowing for lower effective L-DOPA doses, which could be critical for long-term management and reducing L-DOPA-related side effects [2].
The results of the second study assessing the effects on dyskinesia and locomotor activity in L-DOPA primed MPTP marmosets, found that in the primed animals, acute administration of L-DOPA/benserazide alone resulted in a dose-dependent increase in maximal dyskinesia scores, with significant dyskinesia observed at doses of 5/1.25, 7.5/1.875, and 10/2.5 mg/kg. L-DOPA also increased locomotor activity in a dose-dependent manner in these primed animals. When KW-6356 at a dose of 1 mg/kg was co-administered acutely with L-DOPA/benserazide, it also led to increased maximal dyskinesia scores with increasing L-DOPA dosage. However, a crucial observation was that the maximal dyskinesia score induced by the combination of 1 mg/kg of KW-6356 with optimal L-DOPA at a dose of 10 mg/kg was not significantly different from that induced by optimal L-DOPA alone. This indicates that while the combination did induce dyskinesia, KW-6356 did not exacerbate the severity of dyskinesia compared to L-DOPA monotherapy in this acute setting. Furthermore, 1 mg/kg KW-6356 administered alone to primed marmosets induced only minimal dyskinesia while still significantly increasing locomotor activity, suggesting an intrinsic anti-parkinsonian effect with a low inherent dyskinesia risk [2].
Initial results of the third study evaluating the chronic co-administration of KW-6356 and low-dose L-DOPA on dyskinesia revealed a high “L-DOPA pre” dyskinesia level in the primed marmosets. Acute administration of a vehicle resulted in very low dyskinesia, while a low 2.5 mg/kg dose of L-DOPA alone induced mild dyskinesia. When 1 mg/kg KW-6356 was co-administered acutely with this low-dose L-DOPA, it induced mild to moderate dyskinesia. The most significant finding emerged from the chronic co-administration phase: daily administration of 1 mg/kg KW-6356 with low-dose L-DOPA at a dose of 2.5 mg/kg, for 21 days led to an increase in dyskinesia severity, reaching 2.00 ± 0.26 by Day 21, when compared to the low-dose L-DOPA alone. However, critically, the amplitude of this dyskinesia was consistently lower than that induced by an optimal, higher 10 mg/kg dose of L-DOPA in the priming phase. Following a 1-week washout period, the dyskinesia severity observed after subsequent single co-administration returned to levels comparable to those during the chronic administration, indicating a reversible effect.
Figure 1: Changes in A) total disability score and B) total locomotor activity across experimental treatment groups receiving varying doses of KW-6356 and L-DOPA.
In summary, the study demonstrates that KW-6356 effectively potentiates the anti-parkinsonian activity of L-DOPA across a range of doses. Importantly, in dyskinesia-primed marmosets, KW-6356 did not exacerbate dyskinesia when acutely co-administered with L-DOPA. Furthermore, even with chronic co-administration alongside a low dose of L-DOPA, the resulting dyskinesia severity remained significantly lower than the dyskinesia associated with optimal, high-dose L-DOPA monotherapy. These results collectively suggest that KW-6356 offers a promising therapeutic strategy to enhance L-DOPA’s efficacy while potentially mitigating the severe dyskinesia often associated with conventional high-dose L-DOPA regimens, thereby improving the overall management of PD symptoms [2].
Disclaimer
**LAB USE ONLY**
*This information is for educational purposes only and does not constitute medical advice. THE PRODUCTS DESCRIBED HEREIN ARE FOR RESEARCH USE ONLY. All clinical research must be conducted with oversight from the appropriate Institutional Review Board (IRB). All preclinical research must be conducted with oversight from the appropriate Institutional Animal Care and Use Committee (IACUC) following the guidelines of the Animal Welfare Act (AWA).
Citations
[1] Maeda T, Kimura T, Sugiyama K, et al. Randomized controlled trial of KW-6356 monotherapy in patients with early untreated Parkinson’s disease. Parkinsonism Relat Disord. 2023;117:105907. doi:10.1016/j.parkreldis.2023.105907
[2] Ohno Y, Okita E, Kawai-Uchida M, et al. The adenosine A2A receptor antagonist/inverse agonist, KW-6356 enhances the anti-parkinsonian activity of L-DOPA with a low risk of dyskinesia in MPTP-treated common marmosets. J Pharmacol Sci. 2023;152(3):193-199. doi:10.1016/j.jphs.2023.05.001
Metabolite 6 (KW-6356) is sold for laboratory research use only. Terms of sale apply. Not for human consumption, nor medical, veterinary, or household uses. Please familiarize yourself with our Terms & Conditions prior to ordering.




| File Name | View/Download |
| 2026-02-16-Umbrella-Labs-Metabolite6-KW-6356-Certificate-of-Analysis-COA.pdf |  |
| File Name | View/Download |
| 2026-02-05-Umbrella-Labs-Metabolite6-KW-6356-Certificate-of-Analysis-COA.pdf | |
VIEW CERTIFICATES OF ANALYSIS (COA)
Additional information
| Weight | 2 oz |
|---|---|
| Options |


