









ROXADUSTAT POWDER
$29.99 – $109.99Price range: $29.99 through $109.99
Roxadustat is sold for laboratory research use only. Terms of sale apply. Not for human consumption, nor medical, veterinary, or household uses. Please familiarize yourself with our Terms & Conditions prior to ordering.


Also Available In:
 Liquid Option >>
- Description
- Additional information
Description
Roxadustat Nootropic Powder


| CAS Number | 808118-40-3 |
| Other Names | Evrenzo, FG-4592, ASP1517, AZD9941 |
| IUPAC Name | 2-[(4-Hydroxy-1-methyl-7-phenoxyisoquinoline-3-carbonyl)amino]acetic acid |
| Molecular Formula | C₁₉H₁₆N₂O₅ |
| Molecular Weight | 352.35 |
| Purity | ≥99% Pure (LC-MS) |
| Liquid Availability | 30mL liquid (50mg/mL, 1500mg bottle) |
| Powder Availability | 1 gram, 5 grams, 60 capsules (25mg/capsule, 1500mg bottle) |
| Storage | Store at 2º – 8º celsius. |
| Terms | All products are for laboratory developmental research USE ONLY. Products are not for human consumption. |
What is Roxadustat?
Roxadustat is a nootropic compound initially developed as an oral therapy for anemia related to chronic kidney disease. However, its ability to regulate cellular responses to oxygen deprivation has also prompted interest in its potential neurological and neuroprotective applications. Roxadustat functions primarily as a hypoxia-inducible factor prolyl hydroxylase inhibitor (HIF-PHI), preventing the degradation of hypoxia-inducible factor (HIF) and thereby enhancing signaling pathways involved in the body’s adaptive response to low-oxygen conditions. By activating these pathways, roxadustat can affect erythropoietin synthesis, iron utilization, angiogenic processes, and cellular adaptation to hypoxic stress.
Main Research Findings
1) In patients with non-dialysis dependent chronic kidney disease, Roxadustat was found to improve hemoglobin levels and reduce the need for red blood cell transfusion
2) In patients with dialysis dependent chronic kidney disease, Roxadustat was shown to improve hemoglobin levels in a manner similar to clinical standard medications.
Selected Data
1) The research team led by Fishbane et al. conducted the OLYMPUS trial, a large-scale, international, multicenter, randomized, double-blind, placebo-controlled phase 3 investigation intended to assess the efficacy and safety of roxadustat for treating anemia in adults with non–dialysis-dependent chronic kidney disease (NDD-CKD). The study incorporated a screening phase lasting up to 6 weeks, followed by a treatment period of variable length that could continue for as long as 4 years, and concluded with an end-of-study follow-up assessment. The treatment period was scheduled to conclude once a predetermined number of adjudicated cardiovascular events had been reached, allowing data from OLYMPUS to be incorporated into a larger pooled cardiovascular safety analysis that included three phase 3 studies involving patients with NDD-CKD [1].
Participants qualified for enrollment if they were 18 years of age or older, had stage 3–5 CKD with an estimated glomerular filtration rate (eGFR) below 60 ml/min per 1.73 m², were not undergoing dialysis, and demonstrated anemia based on an average of two hemoglobin (Hb) measurements below 10 g/dl obtained at least 7 days apart during the screening period. Additional eligibility requirements included a ferritin concentration of at least 50 mg/L and a transferrin saturation (TSAT) of at least 15%. These criteria enabled the investigators to recruit individuals with clinically meaningful anemia across a range of CKD severity while also including participants with differing levels of available iron. Consequently, the study population represented a relatively broad group of patients with NDD-CKD rather than being limited to individuals with relatively mild renal impairment or well-maintained iron stores.
Following eligibility confirmation, participants were randomized in a 1:1 ratio to receive either oral roxadustat or placebo under double-blind conditions. Randomization was conducted centrally using computer-generated allocation codes and blocks of four, with assignment stratified by country to maintain an appropriate distribution of participants across the international study sites. Patients and investigators remained blinded to treatment allocation. Both roxadustat and placebo were initiated at 70 mg administered orally three times per week, with individual doses separated by a minimum of 2 days and a maximum of 4 days. Treatment doses were subsequently modified according to participants’ Hb concentrations, with adjustments performed every 4 weeks through week 52 and every 8 weeks thereafter. The dosing strategy was intended to achieve and maintain Hb concentrations near 11 g/dl, and the maximum allowable dose was the lower of 3.0 mg/kg or 300 mg per administration. Although treatment assignment was concealed, local study personnel had access to Hb measurements to ensure appropriate monitoring and patient safety [1].
The investigators also established predefined criteria for the use of rescue treatments in participants whose anemia did not respond adequately to the assigned study medication. Intravenous iron was permitted for patients who were unable to tolerate or did not adequately respond to oral iron and who had an Hb concentration below 8.5 g/dl accompanied by ferritin below 100 mg/L or TSAT below 20%. RBC transfusions could be administered whenever the treating investigator considered them medically necessary. ESA therapy was permitted when patients demonstrated insufficient improvement despite at least two dose increases or after reaching the maximum allowable study-drug dose, provided that their Hb was below 8.0 g/dl, iron deficiency or bleeding was not responsible for the reduced Hb concentration, and ESA treatment was considered necessary to decrease the risks associated with RBC transfusion. ESA rescue treatment was discontinued once Hb exceeded 9 g/dl or after 4 weeks of treatment, whichever occurred first. Participants were permitted to receive two ESA rescue cycles; a requirement for a third cycle resulted in permanent discontinuation of the study drug. Similarly, participants who initiated dialysis after randomization and required ESA treatment permanently discontinued study treatment [1].
Clinical and laboratory information was collected at baseline and throughout the treatment period according to a prespecified schedule. Most measurements were obtained every 4 weeks through week 52 and every 8 weeks thereafter. Health-related quality of life was evaluated using the Short Form–36 (SF-36), which was administered at randomization and again at weeks 12, 28, and 52. The primary efficacy outcome was defined as the mean change in Hb from baseline averaged across weeks 28–52, irrespective of whether rescue treatment had been administered. Secondary endpoints evaluated several additional aspects of treatment effectiveness, including Hb response during the first 24 weeks in the absence of rescue therapy, changes in Hb among participants with elevated baseline high-sensitivity C-reactive protein (hsCRP), the proportion of time Hb remained at or above 10 g/dl, the proportion of time Hb remained within the 10–12 g/dl range, changes in LDL cholesterol, the requirement for rescue treatment, RBC transfusion requirements, SF-36 measures, and the rate of eGFR decline. Exploratory assessments examined changes in hepcidin, serum iron, ferritin, total iron-binding capacity (TIBC), TSAT, and blood pressure [1].
2) The research team of Fishbane et al. conducted the ROCKIES trial as an international, randomized, open-label, phase 3 clinical study to evaluate the efficacy and safety of oral roxadustat compared with parenteral epoetin alfa for the treatment of anemia in adults with dialysis-dependent chronic kidney disease (CKD). Roxadustat is an oral hypoxia-inducible factor prolyl hydroxylase (HIF-PH) inhibitor that promotes erythropoiesis by enhancing endogenous erythropoietin production and increasing the availability of iron for red blood cell formation. The primary objective was to determine whether roxadustat was able to produce a clinically meaningful increase in hemoglobin (Hb) that was not inferior to the response produced by epoetin alfa. The investigators also assessed the effects of treatment on iron supplementation, red blood cell transfusion requirements, lipid concentrations, markers of iron metabolism, and adverse events. Following a six-week screening period, participants entered a treatment phase that could continue for as long as four years. The overall duration of the study was dependent on the number of cardiovascular events needed for the planned pooled cardiovascular safety analysis [2].
The study enrolled adults aged 18 years or older who had anemia related to dialysis-dependent CKD. Participants were receiving either hemodialysis or peritoneal dialysis and were required to meet specific laboratory and clinical criteria before randomization. In general, patients had been receiving dialysis for at least 30 days, although a subsequent protocol amendment allowed individuals who had been on dialysis for more than two weeks but no more than four months to participate. Anemia status was established using two Hb measurements taken at least seven days apart. Patients who were not receiving erythropoiesis-stimulating agent (ESA) therapy were required to have an Hb concentration below 10 g/dl, whereas participants already receiving an ESA were required to have an Hb concentration below 12 g/dl. Additional eligibility requirements included a serum ferritin concentration of at least 100 ng/ml and a transferrin saturation (TSAT) of at least 20%. Patients with serious or recently occurring cardiovascular or thrombotic conditions were excluded. These exclusions included New York Heart Association class III or IV congestive heart failure, myocardial infarction, acute coronary syndrome, stroke, seizure, or thrombotic or thromboembolic events occurring within 12 weeks before randomization. Patients with uncontrolled hypertension at the time of randomization were also excluded [2].
Once eligibility was confirmed, participants were randomly allocated in a 1:1 ratio to either oral roxadustat or parenteral epoetin alfa. Randomization was computer generated, stratified by country, and performed using an Interactive Web Response System with blocks of four. Roxadustat was administered three times weekly, with the initial dose determined according to the participant’s previous ESA exposure and, for ESA-naive individuals, body weight. Patients who had previously received ESA therapy generally started roxadustat at doses ranging from 70 to 200 mg three times weekly, depending on their previous ESA dose. Participants who had not previously received an ESA received either 70 mg three times weekly when their dry body weight was 45–70 kg or 100 mg three times weekly when their dry weight exceeded 70 kg but was no more than 160 kg. Throughout treatment, roxadustat doses were adjusted according to a predefined algorithm designed to maintain Hb at approximately 11 ± 1 g/dl. For individuals receiving hemodialysis, administration of roxadustat after completion of the dialysis session was recommended. Participants randomized to epoetin alfa received treatment according to their previous ESA regimen or local prescribing practices. ESA-naive participants were initially treated with 50 IU/kg three times weekly, followed by dose adjustments based on local prescribing information.
Management of additional anemia therapies followed predefined study criteria. Oral iron supplementation was allowed in both groups without specific restrictions. Intravenous iron was permitted for participants receiving roxadustat when the Hb response remained inadequate despite at least two dose increases and laboratory findings suggested insufficient iron availability based on ferritin or TSAT. Patients receiving epoetin alfa could also receive IV iron according to the standard practices and treatment protocols of their local clinics. RBC transfusions were permitted in either treatment group when rapid correction of anemia was considered medically necessary or when the treating investigator determined that transfusion was required to stabilize the patient’s condition. Roxadustat-treated participants could additionally receive temporary ESA rescue therapy if they remained severely anemic despite dose escalation or reached the maximum permitted roxadustat dose. Rescue ESA treatment could be initiated when Hb remained below 8.5 g/dl on two consecutive measurements taken at least five days apart, provided that iron deficiency or bleeding was not responsible for the inadequate response. Rescue treatment was stopped once Hb increased above 9 g/dl or after completion of one four-week course. Participants receiving IV iron or RBC transfusions could continue roxadustat, whereas roxadustat was temporarily withheld during rescue ESA therapy. Permanent discontinuation of study treatment could occur because of patient or investigator preference, an adverse event considered to place the patient at unacceptable risk, severe protocol noncompliance, pregnancy, kidney transplantation, or repeated need for ESA rescue treatment [2].
The principal efficacy measure was the mean change in Hb concentration from baseline averaged across weeks 28–52. This endpoint was analyzed regardless of whether participants required rescue therapy and was evaluated within the intent-to-treat population. The comparison was based on a noninferiority design, with a prespecified margin of −0.75 g/dl. Therefore, roxadustat would be considered noninferior to epoetin alfa if the increase in Hb associated with roxadustat was not more than 0.75 g/dl lower than the increase produced by epoetin alfa. Secondary outcomes were evaluated according to a predefined hierarchical sequence. These outcomes included the average change in Hb between baseline and weeks 28–36 without the need for rescue therapy, the change in LDL cholesterol from baseline to week 24, Hb responses among participants with elevated baseline high-sensitivity C-reactive protein (hsCRP), the percentage of time Hb remained at or above 10 g/dl and within the 10–12 g/dl range, monthly IV iron requirements, and the need for a first RBC transfusion. Additional exploratory outcomes examined changes in serum iron, ferritin, TSAT, total iron-binding capacity (TIBC), total cholesterol, HDL cholesterol, triglycerides, and serum hepcidin [2].
Discussion
1) The research team of Fishbane et al. conducted the OLYMPUS trial, which screened 5,222 individuals, of whom 2,441 were not randomized, primarily because they did not satisfy all of the study’s eligibility requirements. The full analysis population consisted of 2,728 participants, whereas the on-treatment population included 2,760 patients. Baseline demographic and clinical characteristics were generally comparable between the treatment groups. Mean baseline hemoglobin (Hb) was 9.1 g/dl in both the roxadustat and placebo groups. Mean estimated glomerular filtration rate (eGFR) was also similar, measuring 19.7 ml/min per 1.73 m² among participants receiving roxadustat and 20.0 ml/min per 1.73 m² among those receiving placebo. Approximately 58% of participants had both ferritin concentrations greater than 100 mg/L and transferrin saturation (TSAT) values above 20%, indicating that more than half of the study population entered the trial with relatively adequate iron stores [1].
Participants assigned to roxadustat generally remained on treatment for a longer period than those receiving placebo. Mean treatment exposure was 19.62 months in the roxadustat group compared with 15.24 months in the placebo group, while median exposure was 20.80 and 14.57 months, respectively. Roxadustat doses most frequently fell within the range of 40–100 mg administered three times per week, with an average weekly dose of 207.6 mg. Adjustments to treatment dosing were common throughout the study. At least one dose reduction occurred in 87.0% of patients receiving roxadustat compared with 41.9% of those receiving placebo, whereas approximately 90% of participants in both groups underwent at least one dose increase. Despite these adjustments, treatment adherence remained high, with at least 75% compliance reported in 96.1% of roxadustat-treated patients and 96.7% of placebo-treated patients. Discontinuation of study medication before completion was substantially more common in the placebo group, occurring in 58.2% of placebo recipients compared with 36.1% of those treated with roxadustat. A post hoc analysis produced a hazard ratio of 0.49 for treatment discontinuation, corresponding to a 51% lower risk of discontinuation among participants receiving roxadustat [1].
The primary efficacy analysis demonstrated a substantial difference between roxadustat and placebo in the ability to increase hemoglobin concentrations. Although both treatment groups began with an identical mean baseline Hb of 9.1 g/dl, the adjusted least-squares mean increase in Hb averaged over weeks 28–52 was 1.75 g/dl in the roxadustat group, compared with only 0.40 g/dl in the placebo group. The difference between treatments became apparent relatively soon after randomization and remained evident throughout the treatment period. Roxadustat’s effect on Hb was also observed across clinically relevant subgroups. During the first 24 weeks of treatment, 77.0% of patients receiving roxadustat achieved the predefined Hb response compared with just 8.5% of participants receiving placebo. This corresponded to a relative risk of 9.12, demonstrating that patients assigned to roxadustat were substantially more likely to achieve the specified hemoglobin response.
The efficacy of roxadustat was maintained in patients with inflammation as well as in individuals with different levels of baseline iron availability. Among the 411 participants who had elevated high-sensitivity C-reactive protein (hsCRP) concentrations at baseline, the adjusted mean increase in Hb was 1.75 g/dl with roxadustat compared with 0.62 g/dl with placebo, resulting in a treatment difference of 1.13 g/dl. Similar improvements in Hb were observed among participants who were considered iron replete and those who were not iron replete. Roxadustat also increased the amount of time patients maintained clinically meaningful Hb concentrations. During weeks 28–52, interpolated Hb values remained at or above 10 g/dl for approximately 82% of the assessment period in the roxadustat group, compared with 33% in the placebo group. In addition, patients receiving roxadustat maintained Hb concentrations within the 10–12 g/dl range for approximately 70% of the evaluation period, whereas placebo-treated participants remained within this range for only 28% of the time. Collectively, these findings demonstrated that the hemoglobin response to roxadustat was observed across differences in anemia severity, renal function, inflammatory status, and iron availability [1].
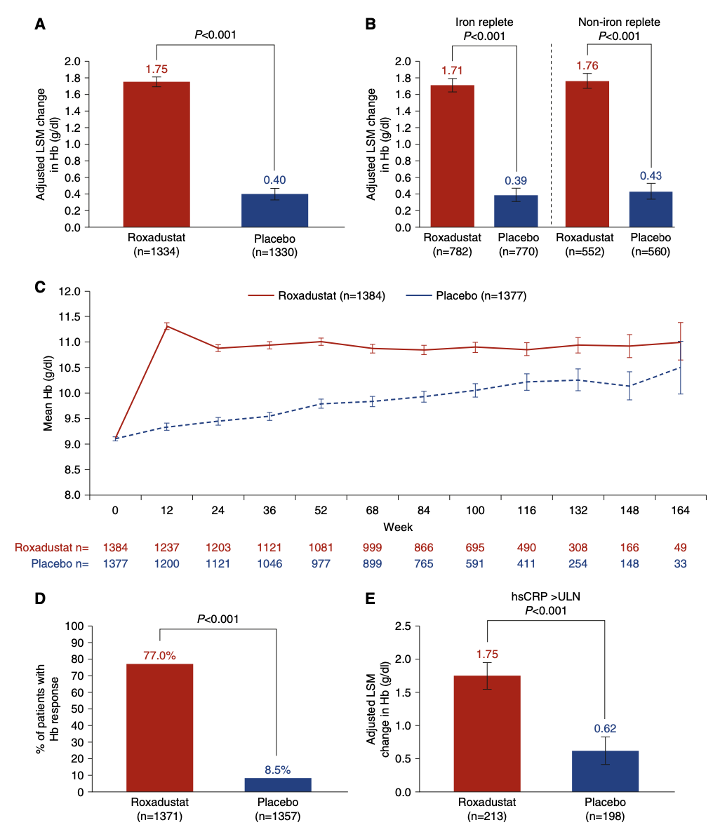
Figure 2: Changes in outcomes measures related to average Hb levels following treatment.
In addition to improving Hb, roxadustat was associated with a significant reduction in LDL cholesterol and a decreased requirement for rescue treatments for anemia. Baseline LDL-C levels were comparable between the groups, measuring 94.50 mg/dl in the roxadustat group and 92.52 mg/dl in the placebo group. By week 24, LDL-C concentrations had fallen by 14.58 mg/dl among participants receiving roxadustat, whereas the placebo group experienced a reduction of only 0.70 mg/dl. This resulted in a treatment difference of −13.88 mg/dl. Roxadustat was also associated with a markedly lower likelihood of requiring rescue therapy. The risk of receiving any first rescue treatment was reduced by 74%, corresponding to a hazard ratio of 0.26. More specifically, roxadustat lowered the risk of requiring red blood cell (RBC) transfusion by 63%, intravenous iron by 59%, and erythropoiesis-stimulating agent (ESA) rescue therapy by 87%. Each of these comparisons reached statistical significance, indicating that the improvement in anemia with roxadustat translated into a reduced need for additional anemia-directed interventions [1].
The exploratory analyses of iron metabolism provided further evidence of changes in iron availability associated with roxadustat treatment. Hepcidin concentrations decreased from baseline by an adjusted least-squares mean of 35.94 ng/ml in the roxadustat group, whereas hepcidin increased by 9.42 ng/ml among placebo-treated participants. The resulting treatment difference was −45.36 ng/ml. Serum iron concentrations increased by 6.63 mg/dl with roxadustat but decreased by 1.07 mg/dl with placebo, resulting in a treatment difference of 7.70 mg/dl. Ferritin concentrations also moved in opposite directions between groups, decreasing by 37.10 mg/L with roxadustat while increasing by 17.45 mg/L with placebo. Similarly, total iron-binding capacity (TIBC) increased by 30.79 mg/dl in the roxadustat group but decreased by 3.82 mg/dl in the placebo group. TSAT, however, did not demonstrate a statistically significant difference between treatments. Taken together, the reductions in hepcidin and ferritin, along with increases in serum iron and TIBC, were consistent with enhanced iron mobilization and greater availability of iron for erythropoiesis.
Overall, the OLYMPUS trial showed that oral roxadustat produced significantly greater improvements in hemoglobin than placebo among patients with anemia associated with non–dialysis-dependent chronic kidney disease (NDD-CKD). The treatment effect was observed across participants with varying degrees of renal impairment, anemia, inflammation, and iron availability. Roxadustat was additionally associated with substantial reductions in RBC transfusions and other rescue therapies, as well as favorable changes in hepcidin and several indicators of iron metabolism. The reduction in LDL-C represented another potentially beneficial treatment effect observed during the study. Based on these findings, the investigators concluded that roxadustat provided an effective oral treatment option for anemia in NDD-CKD and could offer practical advantages because it could be administered orally at home without requiring routine intravenous iron supplementation. Nevertheless, several study limitations should be considered when interpreting the findings, including the unequal rates of treatment discontinuation between groups, the fact that local study personnel were not fully blinded to Hb measurements, and the inability of the individual OLYMPUS trial to provide sufficient statistical power to independently establish cardiovascular safety [1].
2) The research team of Fishbane et al. conducted the ROCKIES trial, initially screening 2,941 individuals and randomizing 2,133 participants into either the roxadustat group or the epoetin alfa group. The intent-to-treat population consisted of 1,051 participants receiving roxadustat and 1,055 receiving epoetin alfa. Almost all randomized participants received at least one dose of their assigned treatment. Baseline demographic and clinical characteristics were generally comparable between the two treatment groups. The mean age of participants was approximately 54 years, with 89% undergoing hemodialysis and approximately 11% receiving peritoneal dialysis. Median baseline Hb concentrations were 10.2 g/dl in the roxadustat group and 10.3 g/dl in the epoetin alfa group. Most participants had previously been treated with an ESA, with the median prior epoetin alfa-equivalent dose being approximately 4,500 IU per week in both groups. Other important baseline characteristics, including diabetes status, cardiovascular history, and duration of dialysis, were similarly distributed between treatment groups [2].
The duration of treatment exposure varied between the two groups, with participants receiving roxadustat treated for a mean of 20.6 months compared with 23.2 months for those receiving epoetin alfa. During the first 52 weeks, the mean roxadustat dose gradually decreased, whereas the epoetin alfa dose remained comparatively consistent. Roxadustat doses between 50 and 150 mg administered three times weekly represented the most common dosing range, resulting in an average weekly dose of approximately 280.6 mg. In comparison, the mean weekly dose of epoetin alfa was approximately 8,656 IU. Adjustments to treatment doses were frequent in both groups, occurring in 92.7% of participants receiving roxadustat and 90.9% of those receiving epoetin alfa. Participants receiving roxadustat commonly required both dose increases and decreases as investigators attempted to maintain Hb concentrations within the specified target range. Despite the need for dose adjustments, substantial treatment noncompliance was rare, occurring in only 0.9% of participants assigned to roxadustat.
The primary efficacy analysis showed that roxadustat was noninferior to epoetin alfa in its ability to increase Hb concentrations. The adjusted least-squares mean change in Hb from baseline, averaged between weeks 28 and 52, was 0.77 g/dl in participants treated with roxadustat compared with 0.68 g/dl among those receiving epoetin alfa. The resulting treatment difference was 0.09 g/dl, supporting the predefined noninferiority criterion. The effect of treatment remained generally consistent across the prespecified subgroup analyses, including participants with different dialysis modalities and varying durations of dialysis. In both treatment groups, Hb concentrations increased primarily during the first 12 weeks and subsequently stabilized, generally remaining between approximately 10.5 and 11.0 g/dl. Additional sensitivity analyses further supported the primary finding that roxadustat provided Hb control comparable with epoetin alfa [2].
Results from the secondary Hb endpoints further demonstrated similar or, in some analyses, greater efficacy with roxadustat. When the effects of rescue therapy were excluded, the adjusted mean increase in Hb from baseline through weeks 28–36 was 0.88 g/dl with roxadustat and 0.74 g/dl with epoetin alfa, corresponding to a treatment difference of 0.14 g/dl. Roxadustat also demonstrated a significantly greater increase in Hb among participants who had elevated baseline hsCRP concentrations, indicating that its erythropoietic effect remained evident in individuals with biochemical evidence of inflammation. Within this subgroup, the least-squares mean difference between treatments was 0.20 g/dl. Roxadustat was also noninferior to epoetin alfa in maintaining Hb concentrations at or above 10 g/dl and within the 10–12 g/dl range. Over the evaluation period, participants receiving roxadustat maintained Hb concentrations of at least 10 g/dl for approximately 79% of the time, compared with approximately 76% among participants treated with epoetin alfa.
In addition to its effects on Hb, roxadustat demonstrated notable effects on lipid concentrations and iron requirements. LDL cholesterol declined by approximately 14.54 mg/dl from baseline through week 24 in the roxadustat group, and this reduction was significantly greater than that observed with epoetin alfa. Roxadustat was also associated with a lower requirement for intravenous iron. From week 36 through the end of the study, participants receiving roxadustat required an average of 58.71 mg of IV iron per month compared with 91.37 mg per month in the epoetin alfa group. Oral iron use was relatively similar between the two groups, suggesting that the difference in IV iron administration was not primarily attributable to substantially different use of oral supplementation. The requirement for a first RBC transfusion was also noninferior with roxadustat. Transfusions occurred in 9.8% of participants receiving roxadustat compared with 13.2% of those treated with epoetin alfa. Overall rescue therapy was required in 12.6% and 13.2% of participants, respectively, although ESA rescue occurred more frequently in the roxadustat group [2].
The findings related to iron metabolism were consistent with the proposed physiological effects of HIF-PH inhibition. Compared with epoetin alfa, roxadustat produced a significantly greater decline in serum hepcidin, with a least-squares mean treatment difference of −28.21 ng/ml. Ferritin concentrations also declined to a greater extent among participants receiving roxadustat. At the same time, serum iron and total iron-binding capacity (TIBC) increased in the roxadustat group, with these changes persisting during longer-term treatment. In contrast, transferrin saturation (TSAT) did not demonstrate a statistically significant difference between treatment groups. Collectively, these findings were interpreted as evidence of increased iron mobilization and availability to support erythropoiesis. Therefore, the lower requirement for IV iron observed with roxadustat occurred alongside changes in several biochemical markers associated with iron metabolism and utilization [2].
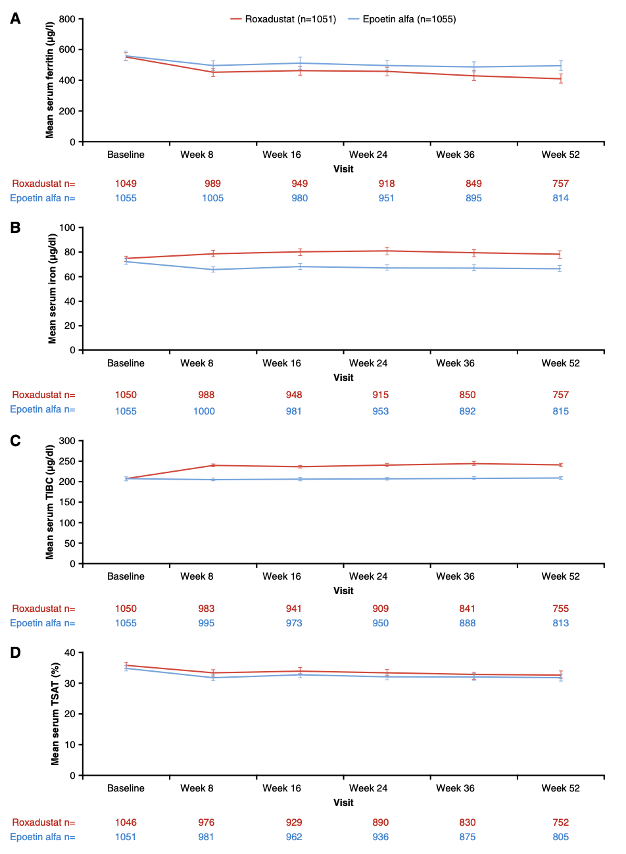
Figure 2: Changes in serum iron parameters following treatment with the experimental compounds.
Overall, the ROCKIES trial demonstrated that oral roxadustat effectively increased and maintained Hb concentrations in individuals with anemia associated with dialysis-dependent CKD, with efficacy that was at least comparable to that of parenteral epoetin alfa. In addition to maintaining Hb, roxadustat was associated with reduced IV iron requirements, lower LDL cholesterol, decreased hepcidin concentrations, and increases in serum iron and TIBC. The treatment was also noninferior to epoetin alfa with respect to the need for RBC transfusion. The overall frequency of adverse events was broadly similar between the two treatment groups, although the greater frequency of treatment discontinuation and certain individual adverse events remained important considerations. Based on these findings, the investigators concluded that roxadustat could provide an effective oral alternative to conventional ESA therapy for patients with dialysis-dependent CKD and anemia, while recognizing that cardiovascular safety could not be fully determined from the ROCKIES trial alone and required assessment within the larger pooled phase 3 clinical program [2].
Disclaimer
**LAB USE ONLY**
*This information is for educational purposes only and does not constitute medical advice. THE PRODUCTS DESCRIBED HEREIN ARE FOR RESEARCH USE ONLY. All clinical research must be conducted with oversight from the appropriate Institutional Review Board (IRB). All preclinical research must be conducted with oversight from the appropriate Institutional Animal Care and Use Committee (IACUC) following the guidelines of the Animal Welfare Act (AWA).
Citations
[1] Fishbane S, El-Shahawy MA, Pecoits-Filho R, et al. Roxadustat for Treating Anemia in Patients with CKD Not on Dialysis: Results from a Randomized Phase 3 Study. J Am Soc Nephrol. 2021;32(3):737-755. doi:10.1681/ASN.2020081150
[2] Fishbane S, Pollock CA, El-Shahawy M, et al. Roxadustat Versus Epoetin Alfa for Treating Anemia in Patients with Chronic Kidney Disease on Dialysis: Results from the Randomized Phase 3 ROCKIES Study. J Am Soc Nephrol. 2022;33(4):850-866. doi:10.1681/ASN.2020111638
Roxadustat is sold for laboratory research use only. Terms of sale apply. Not for human consumption, nor medical, veterinary, or household uses. Please familiarize yourself with our Terms & Conditions before ordering.








| File Name | View/Download |
| 2026-04-20-Umbrella-Labs-Roxadustat-Certificate-of-Analysis-COA.pdf |  |
VIEW CERTIFICATES OF ANALYSIS (COA)
Additional information
| Weight | N/A |
|---|---|
| Dimensions | N/A |
| Options |








