GEPON PEPTIDE 200MG LIQUID SPRAY 15ML BOTTLE (2MG/SPRAY, 200MG TOTAL)
$99.99
Gepon is sold for laboratory research use only. Terms of sale apply. Not for human consumption, nor medical, veterinary, or household uses. Please familiarize yourself with our Terms & Conditions prior to ordering.

- Description
- Additional information
Description
Gepon Peptide Liquid Spray









| CAS Number | 174641-44-2 |
| Other Names | Gepon, HEP-1, HEP1, Hepon |
| IUPAC Name | |
| Molecular Formula | C₇₄H₁₃₂N₂₆O₂₇ |
| Molecular Weight | 1818.025 Da |
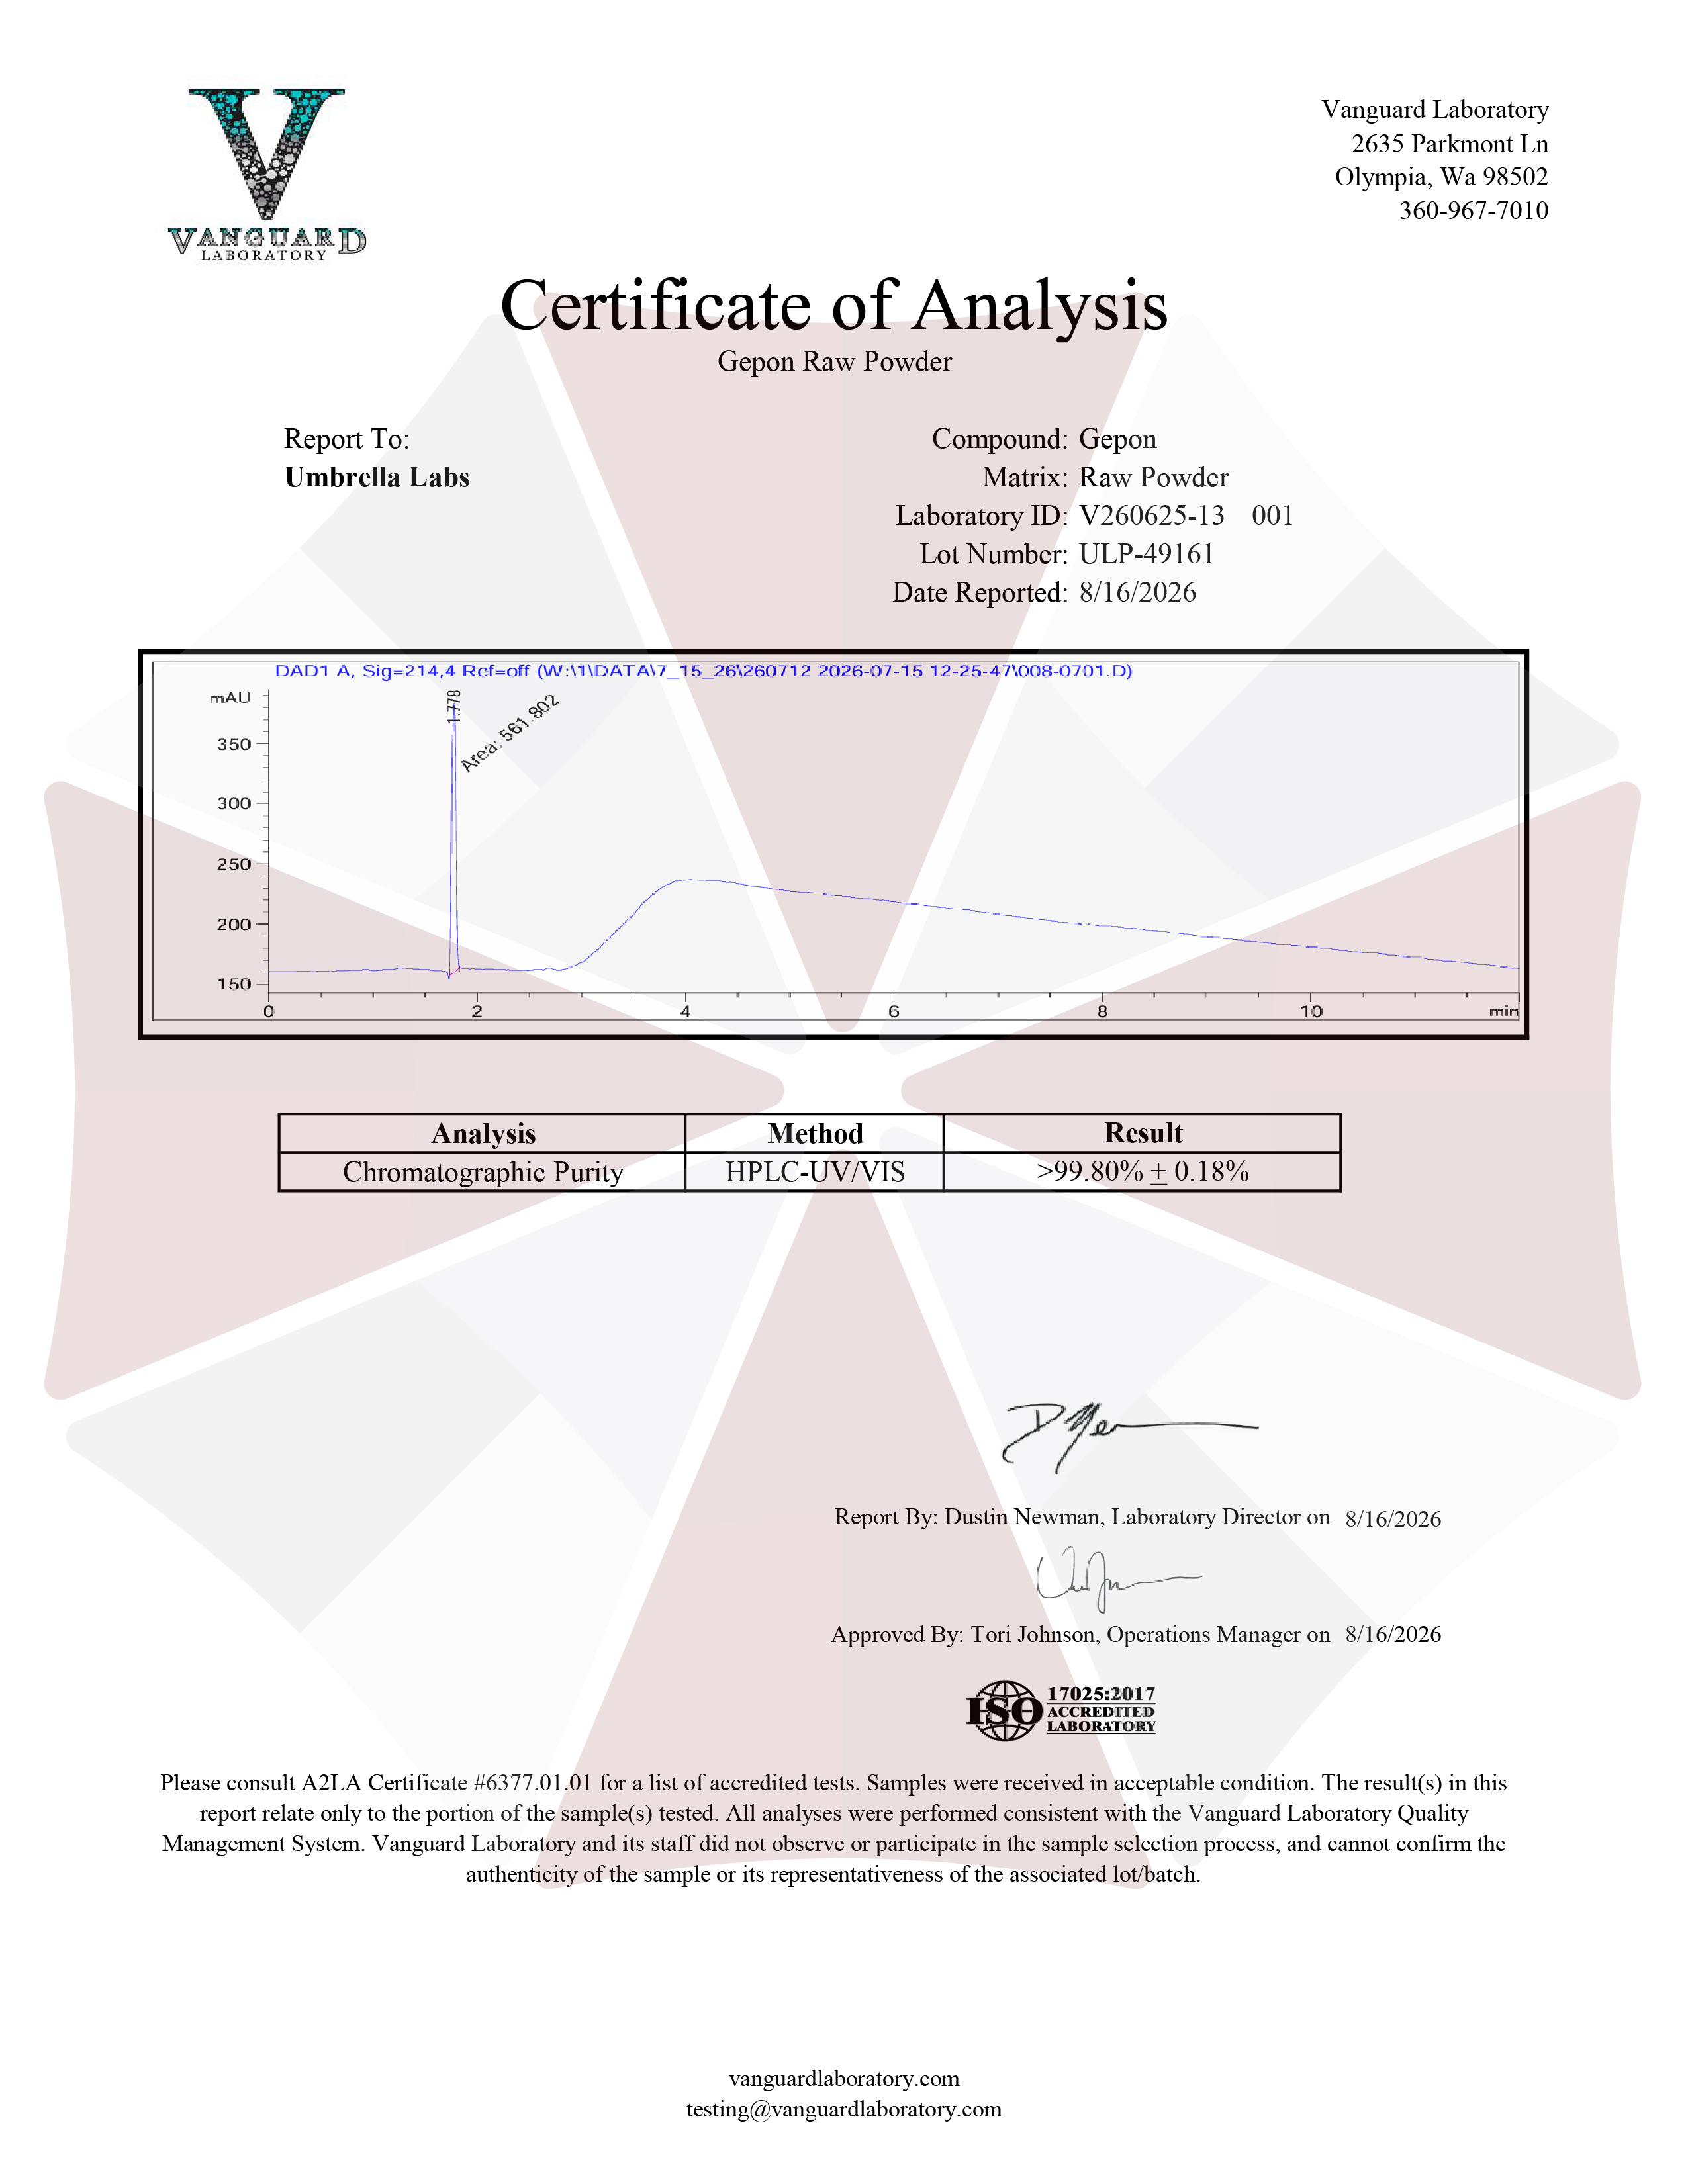
| Purity | ≥99% Pure (LC-MS) |
| Liquid Availability |  15mL (2mg/spray, 200mg total) liquid spray solution |
| Powder Availability | 10 milligrams vial (lyophilized/freeze-dried) |
| Storage Condition | Store cold, keep refrigerated. Do NOT freeze. |
| Terms | All products are for laboratory developmental research USE ONLY. Products are not for human consumption. |
What is Gepon?
Gepon is an immunomodulatory synthetic peptide developed to enhance host defense mechanisms and regulate immune responses. It functions primarily by stimulating the activity of macrophages and other immune cells, promoting the clearance of pathogens and supporting tissue repair processes. Clinically, Gepon has been investigated for its potential in treating conditions associated with impaired immunity, chronic infections, and mucosal damage, particularly within the respiratory and gastrointestinal tracts. By modulating cytokine production and improving epithelial barrier function, the peptide offers both protective and restorative benefits. Its broad spectrum of biological activity highlights its promise as a therapeutic agent in disorders where immune regulation and tissue recovery are critical.
Main Research Findings
1) Gepon was found to act as a potential therapeutic treatment for ulcerative colitis by reducing pro-inflammatory markers linked to colon tissue inflammation.
2) Gepon has the potential to act as a fibroblast modulator, particularly in promoting cell motility and wound repair.
Selected Data
1) This study conducted by Chulkina et al describes the experimental design and methodology used to investigate the effects of Gepon, a synthetic peptide, in a mouse model of dextran sulfate sodium (DSS)-induced colitis. The experimental animals used were C57BL/6 mice that were housed under standard laboratory conditions in an environment that was carefully controlled, with a constant temperature of 22–24 °C, humidity maintained at 55% ± 15%, and a 12-hour light/dark cycle. Mice were provided free access to sterilized chow and water. To establish consistent baseline conditions, the mice were divided randomly into groups of ten animals, ensuring that the average body weight of animals in each group was equivalent [1].
Colitis was induced using DSS, a widely established model of inflammatory bowel disease. Specifically, DSS polymers with a molecular weight of 35–50 kDa were dissolved in sterile drinking water and administered to the mice ad libitum. The treatment protocol involved two cycles of DSS administration: each cycle lasted for five days at a concentration of 2.5%, followed by a five-day interval during which the animals received only plain water. After the final DSS cycle, mice were again given water only. This schedule is consistent with prior methods used in DSS-induced colitis models.
Alongside DSS, some animals received Gepon, which was obtained as a sterile lyophilized powder and prepared fresh in sterile water. The peptide was administered intraperitoneally at a dose of 2.25 mg/kg in a 50 µL volume. Gepon injections were given every two days from the start of the experiment through day 19, covering both DSS cycles as well as the intervening and recovery periods. The study was structured around three experimental groups: a control group receiving only water, a DSS group treated with DSS and vehicle injections, and a DSS + Gepon group receiving both DSS and Gepon. On day 19, all animals were sacrificed for endpoint analysis, and their large intestines were harvested for assessments including colon length, flow cytometric analysis of immune cell populations, and PCR-based gene expression profiling. The experiments were repeated independently twice to ensure reproducibility [1].
Clinical monitoring of colitis severity was conducted daily using a disease activity index (DAI). The DAI combined three parameters: body weight loss, the presence of occult or visible blood in feces, and stool consistency. Each criterion was scored from 1 to 4, producing a maximum possible score of 12 per mouse. Definitions were clearly outlined: loose stool was identified when samples became paste-like upon handling, while diarrhea was marked by the absence of formed stool. Occult blood detection was performed using a benzidine reaction assay, in which feces were mixed with reagents that produce a blue color in the presence of hemoglobin. To minimize false positives, only reactions occurring immediately after reagent addition were considered valid.
For immune cell profiling, colonic leukocytes were isolated using a multistep enzymatic digestion protocol. After removal and flushing with PBS, colon samples were cut into sections, pretreated to remove epithelial cells, then minced and digested with collagenase I, collagenase IV, and DNase to yield single-cell suspensions. These suspensions were filtered through successive mesh strainers to remove debris and enrich for immune cells. The resulting suspensions were then stained with a comprehensive panel of fluorochrome-conjugated antibodies targeting various markers in order to distinguish granulocytes, monocytes, macrophages, dendritic cells, T-cell subsets, and eosinophils. Flow cytometry was conducted on a FACS Aria II instrument after system calibration with beads and compensation controls. Both live/dead staining with DAPI and bead-based normalization were employed to ensure accurate quantification of absolute cell numbers per colon. Between 0.6–1.0 million events were recorded per sample, and results were analyzed using FACSDiva and Cytobank software. Select immune subsets, such as granulocytes and monocytes, were further sorted for downstream applications [1].
To study gene expression, total RNA was extracted from half-colon samples using phenol-chloroform methods and purified with lithium chloride precipitation, which is particularly important to remove residual DSS polysaccharides that can interfere with downstream reactions. The RNA was further processed to cDNA using reverse transcription, and quantitative real-time PCR was carried out with specific primers. Expression levels were normalized to beta-actin (Actb) and further quantified [1].
Additional in vitro experiments assessed the direct effects of Gepon on bone marrow-derived immune cells. Ly6C+ monocytes and Ly6G+ granulocytes were harvested from both control mice and mice undergoing DSS colitis. Bone marrow cells were flushed from femurs and tibias, filtered, and stained for cell-surface markers before FACS sorting. Purified cells were then cultured in DMEM supplemented with fetal bovine serum. Gepon was added at a concentration of 50 µg/mL, and the cells were incubated for 14 hours. Following incubation, the cells were analyzed for gene expression changes via PCR, providing insight into how Gepon modulates immune cell function at a molecular level.
Overall, this framework provides a comprehensive approach to investigating the effect of Gepon in DSS-induced colitis. It combines in vivo treatment regimens with careful clinical scoring, immune cell phenotyping, and molecular analysis, ensuring that both systemic and cellular outcomes of treatment are captured. By incorporating both in vivo and in vitro experiments, the study aims to clarify whether Gepon exerts its therapeutic effects directly on immune cells or through broader systemic mechanisms [1].
2) The study performed by Chulkina et al employed NIH/3T3 fibroblast cells to explore cellular responses to transforming growth factor-beta 1 (TGF-β1) and Gepon. Cells were cultured in high-glucose DMEM supplemented with L-glutamine, sodium pyruvate, calf bovine serum (CBS), and gentamicin, and were maintained at 37 °C in 5% CO₂. For experiments, cells were used only between passages three and six to ensure reproducibility. To prepare for stimulation, cells were grown on type I collagen-coated surfaces, allowed to attach and spread overnight in full serum medium, then adapted for 24 hours in low-serum medium. Treatments with either Gepon, obtained in pharmaceutical-grade purity, or recombinant TGF-β1 were performed in low-serum conditions. A range of antibodies against markers such as α-smooth muscle actin (α-SMA), CD44, ERK1/2, phospho-ERK, and pSMAD2/3 were used for flow cytometry, immunofluorescence, and western blot assays [2].
The CD44 receptor was specifically disrupted in NIH/3T3 cells using CRISPR-Cas9 gene-editing. To reduce off-target effects, the team applied a double-nicking approach combined with a high-fidelity eCas9 nickase mutant (eCas9n). Guide RNAs targeting exon 2 of the mouse CD44 gene were designed and cloned into expression plasmids. NIH/3T3 cells grown on collagen-coated surfaces were transfected with eCas9n and gRNA plasmids using electroporation. After transfection, CD44-negative cells were sorted twice using flow cytometry, reaching purities above 99%. The knockout was verified by staining with fluorescently conjugated anti-CD44 antibodies, ensuring complete receptor deletion for downstream functional assays.
Cell motility was assessed using a scratch assay and measured by the wound healing abilities. Confluent NIH/3T3 monolayers were scratched with a pipette tip, rinsed, and then incubated in fresh low-serum medium with or without Gepon or TGF-β1. Wound closure was monitored by live-cell imaging every two hours over a six-hour period. The width of the scratch area was measured in sequential images, and closure rates were quantified in micrometers per hour. ImageJ software was employed for measurement, and linear regression of wound width reduction over time was used to calculate migration rates [2].
For immunofluorescence assays, cells were cultured on collagen-coated chamber slides, fixed with paraformaldehyde and methanol, and blocked with BSA solution. Primary antibodies against ERK1/2 and phospho-ERK were applied, followed by fluorescent secondary antibodies. In parallel, α-SMA-positive stress fibers were stained using FITC-conjugated antibodies. Cell nuclei were counterstained with DAPI, and samples were mounted with an antifade medium. Confocal microscopy with laser scanning was used to visualize and document subcellular distributions of signaling proteins and cytoskeletal filaments. Green fluorescence intensity from pERK-stained cells was measured using ImageJ macros, enabling quantification of nuclear-to-cytoplasmic distribution ratios [2].
Western blotting further assessed protein expression and activation states. NIH/3T3 cells were lysed in an extraction buffer supplemented with protease and phosphatase inhibitors, and lysates were cleared by centrifugation. Protein concentrations were determined with a BCA assay, and equal amounts were denatured, resolved by SDS-PAGE, and transferred to PVDF membranes. Blots were probed with antibodies against phosphorylated SMAD2/3, phosphorylated ERK1/2, α-SMA, and GAPDH as a loading control. Detection was achieved using horseradish peroxidase-conjugated secondary antibodies and enhanced chemiluminescence reagents, with bands visualized on X-ray film. Densitometric quantification was performed using ImageJ, and values were normalized against GAPDH to control for loading differences.
At the transcript level, quantitative RT-PCR was used to measure expression of fibrosis-related genes including α-sma, col1-α1, and tgf-β1. Cells were seeded on collagen-coated plates, serum-starved, and treated with TGF-β1 or Gepon for 24 hours. Total RNA was extracted using an acid guanidinium thiocyanate–phenol–chloroform method, purified with an RNA extraction kit, and treated with DNase to remove genomic DNA contamination. RNA purity was verified spectrophotometrically, and only samples with OD260/280 ratios greater than 1.8 were used. Complementary DNA was synthesized and amplified by RT-PCR using specific primer pairs. Cycling conditions included denaturation, annealing, and extension, with real-time monitoring via FAM fluorescence. Gene expression was normalized to β-actin levels ensuring reliable quantification of treatment effects on mRNA expression [2].
In summary, this experimental design combined pharmacological treatments, CRISPR-mediated receptor knockout, functional motility assays, protein-level detection, and transcript quantification to investigate the effects of Gepon and TGF-β1 in fibroblasts. The methods allowed precise assessment of cell migration, receptor function, cytoskeletal remodeling, and downstream signaling pathways such as SMAD and ERK. By integrating multiple complementary approaches including imaging, western blotting, and RT-PCR to provide a framework for the analysis of how Gepon modulates fibroblast activity and fibrogenic signaling, particularly in relation to CD44-mediated responses [2].
Discussion
1) Researchers Chulkina et al investigated the therapeutic potential of Gepon in a mouse model of DSS-induced colitis. Colitis was induced by administering 2.5% DSS in two cycles, each lasting five days and separated by five-day recovery intervals. This protocol caused severe intestinal inflammation in mice, leading to weight loss, diarrhea, and rectal bleeding, as is characteristic of DSS colitis. In untreated animals, these symptoms progressed significantly, while Gepon administration provided notable protection. During the second DSS cycle, mice in the untreated group lost around 14% of their body weight, compared to less than 6% in Gepon-treated animals. Similarly, DAI scores reached 5–6 in untreated DSS mice but were significantly lower in the treated group. Moreover, Gepon improved survival rates and prevented colon shortening, a hallmark of DSS colitis. While untreated colitis reduced colon length to 7.0 cm, compared to 9.6 cm in healthy mice, Gepon preserved colon length to an average of 8.5 cm, demonstrating substantial protective effects against tissue damage [1].
To understand the molecular mechanisms, the study examined cytokine expression in colon tissues. DSS colitis was associated with strong upregulation of pro-inflammatory mediators, including interleukin-1β (Il1b), interleukin-6 (Il6), tumor necrosis factor-alpha (Tnf), and inducible nitric oxide synthase (Nos2). Compared to healthy mice, DSS treatment caused a 12-fold increase in Il1b, a 29-fold increase in Il6, a three-fold rise in Tnf, and a six-fold rise in Nos2 mRNA levels. Gepon treatment markedly reduced these elevations, lowering Il1b, Il6, and Nos2 transcripts by approximately threefold each. Interestingly, anti-inflammatory factors such as transforming growth factor-beta 1 (Tgfb1), interleukin-10 (Il10), and arginase-1 (Arg1) were also upregulated in DSS colitis by two-, seven-, and seven-fold, respectively, indicating a counter-regulatory immune response. However, Gepon did not significantly affect the levels of these anti-inflammatory mediators, suggesting its primary mechanism was suppression of pro-inflammatory signaling rather than enhancement of anti-inflammatory pathways.
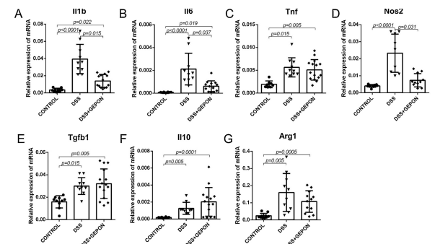
Figure 1: Changes in the levels of pro-inflammatory genes in colonic genes.
Flow cytometric analysis provided insight into immune cell infiltration in colonic tissues. In healthy mice, colons contained about 0.3 × 10^6 CD45+ leukocytes. Following DSS-induced inflammation, this number rose nearly four-fold to 1.2 × 10^6. Gepon treatment significantly reduced leukocyte infiltration, lowering the count to 0.7 × 10^6. Detailed phenotyping revealed that DSS colitis expanded multiple immune compartments, including granulocytes, monocytes, macrophages, eosinophils, and T-cell subsets. The most pronounced effects of Gepon were observed on innate immune cells, specifically Ly6G+ granulocytes and Ly6C+ monocytes. Granulocyte numbers rose from 3.7 × 10^3 in healthy colons to 5.6 × 10^4 in DSS colitis, but Gepon reduced this to 2.5 × 10^4 [1].
Similarly, monocyte counts increased from 7.6 × 10^3 in controls to 9.3 × 10^4 in DSS colitis, and were reduced to 4.5 × 10^4 under treatment. By contrast, Gepon did not significantly affect macrophage, eosinophil, or T-cell numbers. Importantly, DSS colitis disrupted the normal monocyte-to-macrophage balance in colonic tissue, raising the ratio fivefold compared to healthy conditions. Gepon restored this balance by halving the ratio, thereby reducing excessive monocyte accumulation without altering macrophage populations [1].
To explore cell-specific effects, the researchers sorted granulocytes, monocytes, and macrophages from inflamed colonic tissues and analyzed their gene expression. The purity of sorted populations was high, exceeding 85% for each subset. Inflammatory markers, including Tnf and Nos2, were strongly expressed in both Ly6C+ monocytes and Ly6G+ granulocytes. Gepon treatment suppressed Tnf expression by over fourfold in monocytes and nearly fourfold in granulocytes. Similarly, Nos2 mRNA levels were reduced by more than fourfold in both populations. These results indicated that Gepon directly inhibits pro-inflammatory gene expression in infiltrating innate cells. In contrast, macrophages, though abundant in inflamed colons, did not show significant changes in Tnf or Nos2 expression under Gepon treatment, suggesting selective effects on monocytes and granulocytes rather than broad suppression of all myeloid subsets.
The study also examined anti-inflammatory genes within sorted populations. Arg1, an enzyme linked to resolution of inflammation, was elevated in both monocytes and macrophages during colitis. Gepon reduced Arg1 expression in monocytes by about 2.5-fold, but had no effect in macrophages. Meanwhile, Tgfb1 transcription was detectable in monocytes and macrophages but unaffected by treatment, while it remained nearly absent in granulocytes. Thus, the modulatory role of Gepon appeared to be targeted toward reducing excessive pro-inflammatory activity rather than enhancing anti-inflammatory outputs in myeloid cells [1].
Finally, in vitro experiments provided direct evidence of Gepon’s action on monocytes. Purified Ly6C+ monocytes from DSS-treated mice were cultured and exposed to Gepon, resulting in significantly lower expression of Il1b and Il6 mRNA compared to untreated controls. This finding reinforced the in vivo observations, demonstrating that Gepon directly downregulates inflammatory cytokine production in monocytes.
Taken together, the findings highlight the protective role of Gepon against DSS-induced colitis through multiple mechanisms. The compound attenuated clinical symptoms such as weight loss, bleeding, diarrhea, and colon shortening, while reducing overall mortality. At the molecular level, it suppressed the transcription of key pro-inflammatory cytokines and enzymes without interfering with compensatory anti-inflammatory mediators. At the cellular level, Gepon diminished the infiltration of leukocytes into the colon, especially immature granulocytes and inflammatory monocytes, while restoring the balance between monocytes and macrophages. Importantly, the action of the compound was selective, targeting pro-inflammatory cells and their cytokine expression rather than globally suppressing immune function. These results suggest that Gepon may exert therapeutic effects in inflammatory bowel disease by dampening pathological inflammation while sparing protective immune responses, offering a promising avenue for further preclinical and potentially clinical exploration [1].
2) Researchers Chulkina et al investigated how Gepon, an immunomodulatory agent, influences fibroblast activation and wound healing mechanisms compared to TGF-β1, a well-known regulator of fibroblast differentiation and function. Fibroblast activation is typically characterized by the induction of α-SMA, increased collagen expression, and upregulation of TGF-β1 itself. Using NIH/3T3 murine fibroblasts, the study systematically examined the transcriptional, protein-level, and functional effects of Gepon relative to TGF-β1 [2].
The initial experiments focused on gene transcription. Fibroblasts treated with either Gepon or TGF-β1 showed increased expression of α-sma and collagen type I α1 (col1α1). Specifically, TGF-β1 induced a 3.2-fold increase in α-sma mRNA and a two-fold increase in col1α1, while Gepon elicited more modest increases of 1.6- and 1.4-fold, respectively. However, only TGF-β1 elevated its own gene expression (tgf-β1 mRNA), while Gepon had no effect on this target. These transcriptional changes were mirrored at the protein level. After 48 hours of treatment, both agents induced α-SMA protein synthesis and stress fiber formation, as confirmed by confocal microscopy and Western blotting. TGF-β1 was more potent, raising the percentage of α-SMA positive cells to 34%, compared to 15% in Gepon-treated cultures. Collectively, these results demonstrate that Gepon can activate fibroblasts, though less efficiently than TGF-β1, and without stimulating endogenous TGF-β1 transcription [2].
To better understand the signaling mechanisms involved, the researchers investigated both canonical and non-canonical TGF-β1 pathways. The canonical SMAD-dependent cascade is normally initiated by phosphorylation of SMAD2/3 proteins following TGF-β1 receptor engagement. Consistent with previous reports, TGF-β1 treatment caused robust and time-dependent phosphorylation of SMAD2, peaking at 60 minutes. In contrast, Gepon exposure only caused minimal and statistically insignificant increases in SMAD2 phosphorylation, suggesting that it does not effectively trigger the canonical pathway. Thus, Gepon’s fibroblast-activating effects must rely on alternative signaling routes.
Attention was then turned to SMAD-independent pathways, particularly the Ras/Raf/MEK/ERK cascade, which plays central roles in proliferation, motility, and survival. Both TGF-β1 and Gepon rapidly activated ERK1/2 kinases, as shown by microscopy and Western blotting. Phosphorylation of ERK1 and ERK2 peaked at 5 minutes and returned to baseline by 60 minutes. While TGF-β1 induced slightly higher levels of phosphorylation than Gepon, both agents clearly engaged this non-canonical signaling axis. The downstream effects were evident in c-fos transcription, a target gene of ERK1/2 signaling. Both treatments induced strong, transient increases in c-fos expression, reaching three- to fourfold within 30 minutes. Importantly, this activation was blocked by the ERK1/2 inhibitor PD0325901, confirming the pathway’s role in mediating Gepon and TGF-β1 signaling [2].
Functional assays highlighted differences between the two agents. Fibroblast motility, a crucial component of wound healing, was evaluated using a scratch assay. TGF-β1 had no significant effect on the rate of wound closure compared to control, while Gepon increased cell motility by approximately 25%. This finding suggests that Gepon promotes wound healing not only by stimulating fibroblast activation but also by directly enhancing their migration, a property not shared by TGF-β1 in this context.
Finally, the potential role of CD44, a surface receptor involved in cell-extracellular matrix interactions and migration, was examined. Using CRISPR/Cas9, NIH/3T3 fibroblasts lacking CD44 were generated. Strikingly, basal cell motility was markedly enhanced in CD44 knockout fibroblasts, with migration rates nearly double those of wild-type cells. However, the absence of CD44 did not affect Gepon or TGF-β1 signaling. Both agents continued to induce α-SMA expression, collagen transcription, and ERK1/2 activation, with similar dynamics as in wild-type cells. This indicated that CD44 is not the receptor mediating Gepon’s effects. Nevertheless, the dramatic increase in baseline motility in knockout cells underscores CD44’s regulatory role in fibroblast migration and suggests possible cross-talk with Gepon-induced pathways [2].
In conclusion, the study reveals that Gepon activates fibroblasts through mechanisms distinct from TGF-β1. Both agents upregulate α-SMA and collagen, but Gepon does so without inducing endogenous TGF-β1 expression or strongly engaging the SMAD-dependent signaling cascade. Instead, Gepon predominantly acts through non-canonical ERK1/2 pathways, leading to downstream c-fos activation. Importantly, Gepon enhances fibroblast motility, a unique property that likely contributes to its clinical efficacy in wound healing. CD44, while critical for regulating baseline cell migration, is not required for Gepon’s signaling, indicating the involvement of alternative, yet unidentified receptors. Together, these findings establish Gepon as a fibroblast modulator with overlapping but distinct effects from TGF-β1, particularly in promoting cell motility and wound repair [2].
Disclaimer
**LAB USE ONLY**
*This information is for educational purposes only and does not constitute medical advice. THE PRODUCTS DESCRIBED HEREIN ARE FOR RESEARCH USE ONLY. All clinical research must be conducted with oversight from the appropriate Institutional Review Board (IRB). All preclinical research must be conducted with oversight from the appropriate Institutional Animal Care and Use Committee (IACUC) following the guidelines of the Animal Welfare Act (AWA).
Citations
[1] Chulkina MM, Pichugin AV, Ataullakhanov RI. Pharmaceutical grade synthetic peptide Thr-Glu-Lys-Lys-Arg-Arg-Glu-Thr-Val-Glu-Arg-Glu-Lys-Glu ameliorates DSS-induced murine colitis by reducing the number and pro-inflammatory activity of colon tissue-infiltrating Ly6G+ granulocytes and Ly6C+monocytes. Peptides. 2020;132:170364. doi:10.1016/j.peptides.2020.170364
[2] Chulkina M, Negmadjanov U, Lebedeva E, et al. Synthetic peptide TEKKRRETVEREKE derived from ezrin induces differentiation of NIH/3T3 fibroblasts. Eur J Pharmacol. 2017;811:249-259. doi:10.1016/j.ejphar.2017.06.033
PEPTIDES PREFER THE COLD
Keep peptide vials refrigerated at all times to reduce peptide bond breakdown. DO NOT FREEZE. Most peptides, especially shorter ones, can be preserved for weeks if careful.
Always swab the top of the vial with an alcohol wipe, rubbing alcohol or 95% ethanol before use.
Before drawing solution from any dissolved peptide vial, fill the pin with air to the same measurement you will be filling with solution, ie. if you plan to take 0.1 ml, first fill the pin with 0.1ml of air, push the air into the vial, and then draw the peptide back up to the 0.1 ml marker. Doing so will maintain even pressure in the vial. Always remember to remove air bubbles from the pin by flicking it gently, pin side up, and pushing bubbles out. In addition, push out a tiny amount of solution to ensure there is no air left in the metal tip.
ONLY MIX WITH STERILE BACTERIOSTATIC WATER
The purity and sterility of bacteriostatic water are essential to prevent contamination and to preserve the shelf-life of dissolved peptides.
Push the pin through the rubber stopper at a slight angle, so that you inject the bacteriostatic water toward the inside wall of the vial, not directly onto the powder.
Lyophilized peptide should be stored at -20°C (freezer), and the reconstituted peptide solution at 4°C (refrigerated). Do not freeze once reconstituted.
NEVER SHAKE A VIAL TO MIX.
Air bubbles are unfavorable to the stability of proteins.
Gepon is sold for laboratory research use only. Terms of sale apply. Not for human consumption, nor medical, veterinary, or household uses. Please familiarize yourself with our Terms & Conditions prior to ordering.




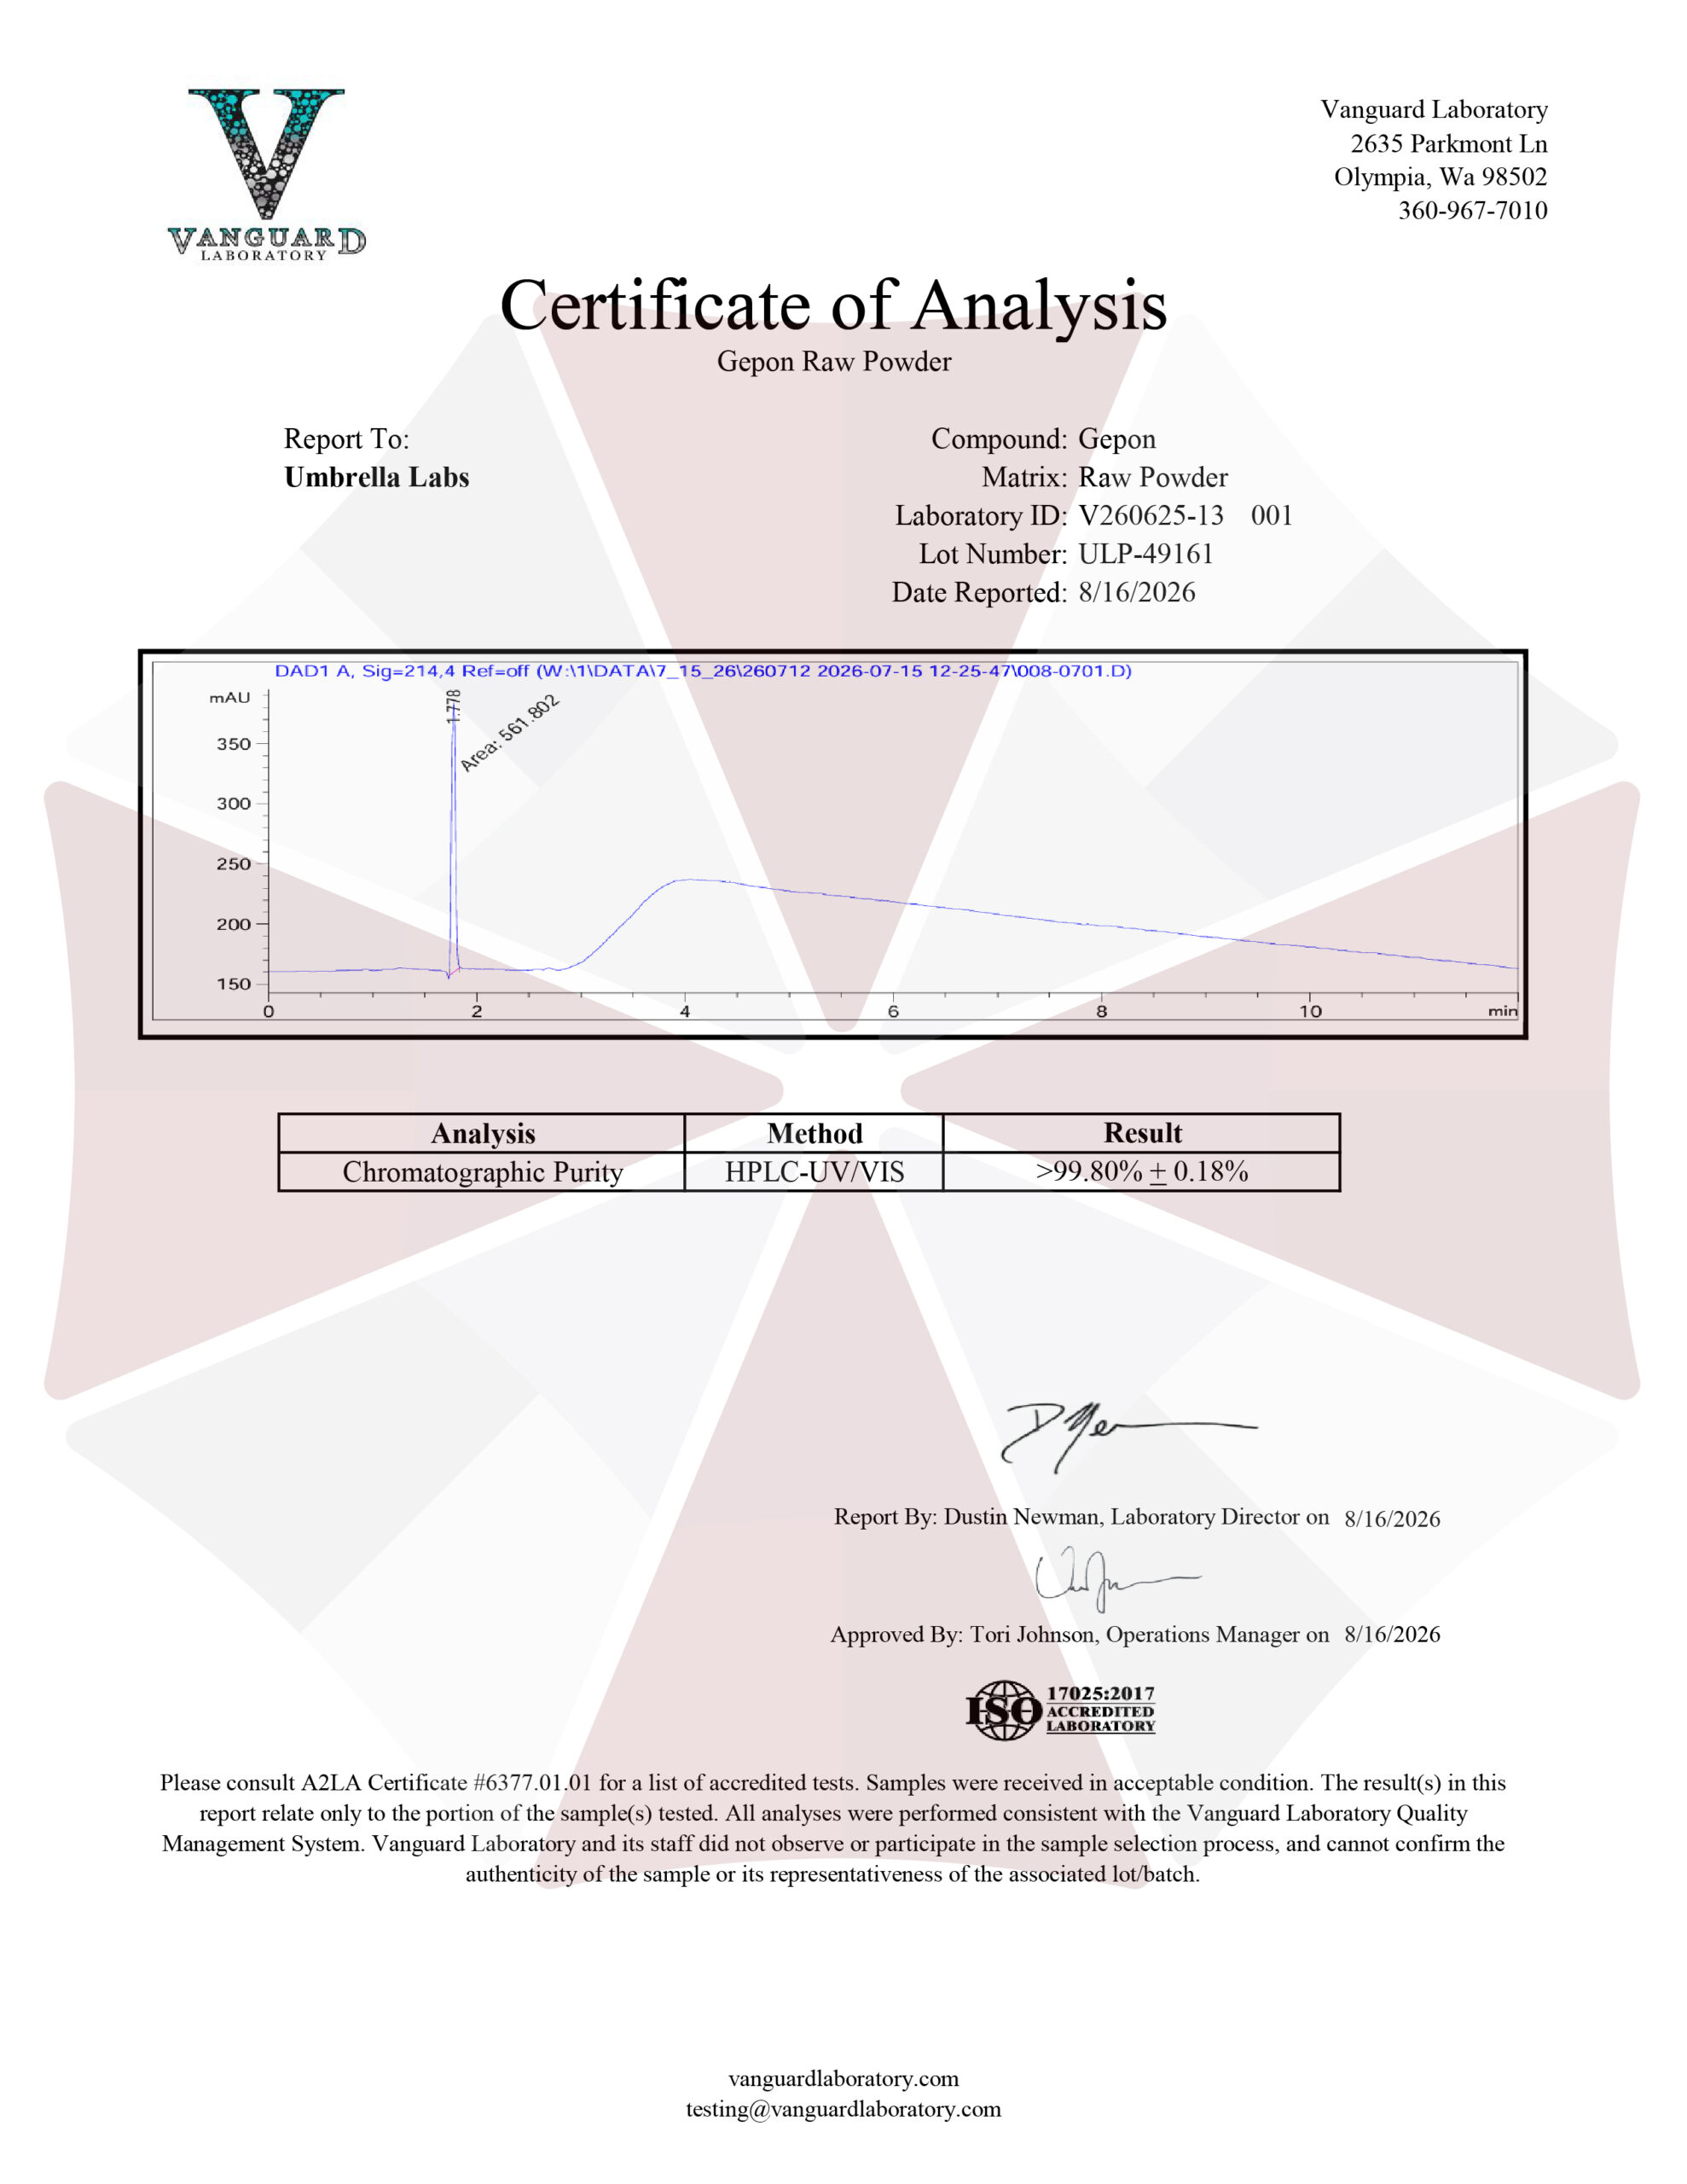
| File Name | View/Download |
| 2026-08-16-UmbrellaLabs-Gepon-Certificate-of-Analysis-COA.pdf |  |
VIEW CERTIFICATES OF ANALYSIS (COA)
Additional information
| Options |
|---|